1,267 posters, 47 videos, 13 topics, 4 sessions, 853 authors
ePostersLive by SciGen Technologies S.A. All rights reserved.
SOHO 2026 Annual Meeting
September 9 - 12, 2026 | George R. Brown Convention Center, Houston, Texas

MM - 1185
Smoldering Multiple Myeloma With High-Risk Cytogenetics Unmasked in a Young Patient With Seronegative Systemic Sclerosis and Severe Pulmonary Arterial Hypertension
Poster Presenter
Authors
Part of Topic
Multiple Myeloma (MM)
Smoldering Multiple Myeloma With High-Risk Cytogenetics Unmasked in a Young Patient With Seronegative Systemic Sclerosis and Severe Pulmonary Arterial Hypertension
A.D. MALENDA1,2, D.A. ȘERBU1,2, E. PÎRVU1,2, D. GRASU1,2, M. BĂCANU1,2, V.M. POPOV1 and M. ANDREESCU1,2
1.Colentina Clinical Hospital, Bucharest, Romania
2.Titu Maiorescu University, Bucharest, Romania
CONTEXT
The recurrent observation of monoclonal gammopathy in systemic sclerosis (SSc) has raised questions about shared immune mechanisms, yet the nature of this association remains incompletely understood.
Proposed links include chronic B-cell stimulation driven by persistent autoantigen exposure, IL-6–mediated plasmacytic expansion, endothelial injury, and shared profibrotic pathways, providing a biological framework through which autoimmune vasculopathy and plasma cell clonal evolution may intersect.
Fig.1. Right third digit showing a painless ulcer with hemorrhagic crust and periungual purulent collection.
Fig.2&3. Right-hand CT. Distal phalanx of the third digit with a small osteolytic defect, cortical disruption suggestive of fracture, focal osseous erosions, and lateral exostosis; no pathological enhancement or significant surrounding inflammatory changes.
PATIENT
•A 38-year-old woman, followed since 2021 for Raynaud phenomenon, developed progressive SSc features, including digital ischemia and ulceration, sclerodactyly, cutaneous sclerosis, and severe vascular/cardiopulmonary involvement.
•Serology remained persistently negative (ANA, SSc panel, U1-RNP), whereas nailfold capillaroscopy revealed capillary dilation, hemorrhages, megacapillaries, and architectural disorganization consistent with an active SSc pattern. Skin biopsy demonstrated dermal collagen thickening, supporting seronegative SSc.
•In 2024, incidental findings revealed an IgG-λ monoclonal band, serum λ FLC 97.77 mg/L (κ/λ, 0.08), with subsequent hematologic workup leading to presumed MGUS after marrow biopsy refusal. In 2026, hospitalization for severe precapillary pulmonary arterial hypertension and moderate-to-large pericardial effusion prompted hematologic reassessment.
•Right-heart catheterization showed PAP of 86/49 mmHg and PAWP of 10 mmHg. HRCT showed no ILD, with severely reduced DLCO supporting SSc-associated pulmonary vasculopathy.
•Bone marrow biopsy confirmed approximately 20%–25% λ-restricted clonal plasma cells (CD138⁺, MUM1⁺, weak cyclin D1+ , CD56−). FISH demonstrated CKS1B/1q21 amplification and IGH rearrangement in 100% of analyzed cells, without t(4;14), t(11;14), t(14;16), TP53 deletion, or ATM abnormalities.
•Serum studies showed IgG-λ monoclonality, M-spike 2.6 g/dL, IgG 3729 mg/dL, λ FLC 187.74 mg/L, and κ/λ, 0.06; urine immunofixation confirmed λ light chains and Bence-Jones proteinuria.
•Computed tomography imaging showed no suspicious osseous lesions, and no CRAB/SLiM criteria were met, establishing IgG-λ SMM with high-risk cytogenetic features.
•There was no histopathologic evidence of systemic AL amyloidosis on multisite surrogate-tissue biopsy.
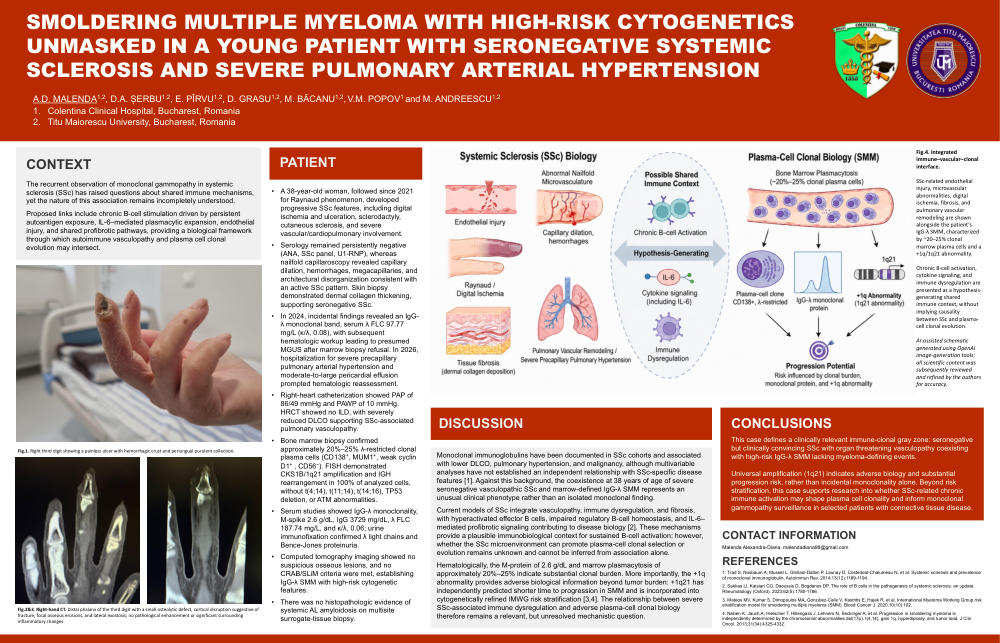
Fig.4. Integrated immune–vascular–clonal interface.
SSc-related endothelial injury, microvascular abnormalities, digital ischemia, fibrosis, and pulmonary vascular remodeling are shown alongside the patient’s IgG-λ SMM, characterized by ~20–25% clonal marrow plasma cells and a +1q/1q21 abnormality. Chronic B-cell activation, cytokine signaling, and immune dysregulation are presented as a hypothesis-generating shared immune context, without implying causality between SSc and plasma-cell clonal evolution.
DISCUSSION
Monoclonal immunoglobulins have been documented in SSc cohorts and associated with lower DLCO, pulmonary hypertension, and malignancy, although multivariable analyses have not established an independent relationship with SSc-specific disease features [1]. Against this background, the coexistence at 38 years of age of severe seronegative vasculopathic SSc and marrow-defined IgG-λ SMM represents an unusual clinical phenotype rather than an isolated monoclonal finding.
Current models of SSc integrate vasculopathy, immune dysregulation, and fibrosis, with hyperactivated effector B cells, impaired regulatory B-cell homeostasis, and IL-6–mediated profibrotic signaling contributing to disease biology [2]. These mechanisms provide a plausible immunobiological context for sustained B-cell activation; however, whether the SSc microenvironment can promote plasma-cell clonal selection or evolution remains unknown and cannot be inferred from association alone.
Hematologically, the M-protein of 2.6 g/dL and marrow plasmacytosis of approximately 20%–25% indicate substantial clonal burden. More importantly, the +1q abnormality provides adverse biological information beyond tumor burden: +1q21 has independently predicted shorter time to progression in SMM and is incorporated into cytogenetically refined IMWG risk stratification [3,4]. The relationship between severe SSc-associated immune dysregulation and adverse plasma-cell clonal biology therefore remains a relevant, but unresolved mechanistic question.
CONCLUSIONS
This case defines a clinically relevant immune-clonal gray zone: seronegative but clinically convincing SSc with organ threatening vasculopathy coexisting with high-risk IgG-λ SMM lacking myeloma-defining events.
Universal amplification (1q21) indicates adverse biology and substantial progression risk, rather than incidental monoclonality alone. Beyond risk stratification, this case supports research into whether SSc-related chronic immune activation may shape plasma cell clonality and inform monoclonal gammopathy surveillance in selected patients with connective tissue disease.
CONTACT INFORMATION
Malenda Alexandra-Diana, malendadiana98@gmail.com
REFERENCES
1. Trad S, Nosbaum A, Musset L, Ghillani-Dalbin P, Launay D, Costedoat-Chalumeau N, et al. Systemic sclerosis and prevalence of monoclonal immunoglobulin. Autoimmun Rev. 2014;13(12):1189-1194.
2. Sakkas LI, Katsiari CG, Daoussis D, Bogdanos DP. The role of B cells in the pathogenesis of systemic sclerosis: an update. Rheumatology (Oxford). 2023;62(5):1780-1786.
3. Mateos MV, Kumar S, Dimopoulos MA, González-Calle V, Kastritis E, Hajek R, et al. International Myeloma Working Group risk stratification model for smoldering multiple myeloma (SMM). Blood Cancer J. 2020;10(10):102.
4. Neben K, Jauch A, Hielscher T, Hillengass J, Lehners N, Seckinger A, et al. Progression in smoldering myeloma is independently determined by the chromosomal abnormalities del(17p), t(4;14), gain 1q, hyperdiploidy, and tumor load. J Clin Oncol. 2013;31(34):4325-4332.