1,267 posters, 47 videos, 13 topics, 4 sessions, 853 authors
ePostersLive by SciGen Technologies S.A. All rights reserved.
SOHO 2026 Annual Meeting
September 9 - 12, 2026 | George R. Brown Convention Center, Houston, Texas

MM - 744
Nonrelapse Mortality Across Anito-cel and Other BCMA-Targeted Therapies in Relapsed/Refractory Multiple Myeloma: A Systematic Review and Meta-Analysis
Poster Presenter
Authors
Part of Topic
Multiple Myeloma (MM)
Non-Relapse Mortality across Anito-cel and other BCMA-Targeted Therapies in Relapsed/Refractory Multiple Myeloma (RRMM): A Systematic Review and Meta-Analysis
P. Forsberg, A.S. Rosenberg, A. Ray, J. Ting, K. Hasegawa, P. Mitra, A. Kostic, S. Kanters, D. Wennersbusch, C.L. Freeman
Colorado Blood Cancer Institute, Denver, CO, USA; University of California, Davis School of Medicine, Sacramento, CA, USA; Arcellx, Inc., Redwood City, CA, USA; Kite, A Gilead Company, Santa Monica, CA, USA; RainCity Analytics, Vancouver, BC, Canada; H. Lee Moffitt Cancer Center, Tampa, FL, USA
OBJECTIVE
To estimate and compare non-relapse mortality (NRM) associated with BCMA-targeted therapies among patients with relapsed/refractory multiple myeloma (RRMM), using evidence from clinical trials and real-world studies.
BACKGROUND
Anitocabtagene autoleucel (anito-cel) is an investigational BCMA-targeted CAR T-cell therapy that has shown promising results in patients with 4L+ RRMM in the phase 2 iMMagine-1 trial.
NRM captures deaths not attributable to disease progression. Although anito-cel demonstrated a favorable safety profile in iMMagine-1, its NRM has yet to be compared with other BCMA-targeted therapies.
To address this evidence gap, we conducted a systematic review and meta-analysis of clinical trials and real-world studies reporting NRM for BCMA-targeted therapies.
METHODS
We systematically searched databases and conferences for studies of BCMA-targeted therapies in RRMM. Eligible studies were randomized/non-randomized trials or observational studies of patients with at least 2 prior lines of therapy published from 2012 to 2025.
Pooled NRM proportions were estimated using random-effects meta-analysis, adjusting for covariates. Informed by previous literature, 9 covariates were identified: treatment type, line of therapy (LOT), treatment era, follow-up time, study setting, prior BCMA exposure, bridging therapy, age and progression-free survival. Univariate analyses identified significant covariates for selection in the multivariate analyses.
The base case analysis was restricted to clinical trials with follow-up within plus or minus 3 months of the iMMagine-1 trial's median follow-up of 15.9 months, which accounts for the confounding relationship between follow-up time and NRM (longer follow-up time allows for more events). Deaths occurring after salvage therapy or of unknown cause were also excluded.
Causes of death were compared across all trials by Pearson chi-squared test, excluding unknown causes and using categories previously cited by Cordas Dos Santos et al., 2024.
Sensitivity analyses were also conducted relaxing the follow-up restriction and incorporating real-world studies.
RESULTS
Fifty-three records reporting on 30 studies were identified, including 14 clinical trials and 16 real-world studies.
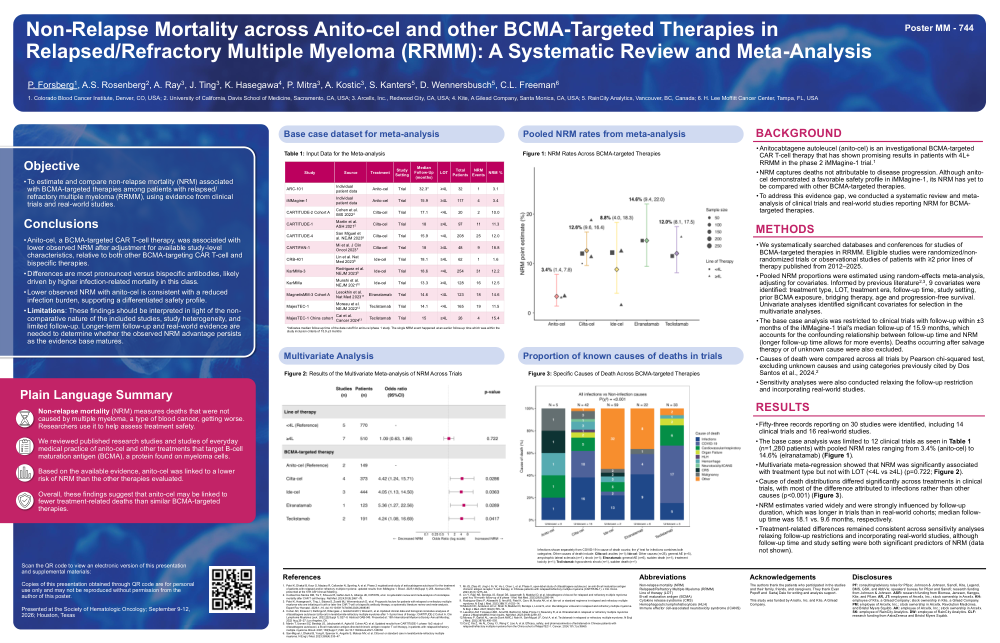
The base case analysis was limited to 12 clinical trials (n=1,280 patients) with pooled NRM rates ranging from 3.4% (anito-cel) to 14.6% (elranatamab).
Multivariate meta-regression showed that NRM was significantly associated with treatment type but not with line of therapy (fewer than 4L versus 4L or later) (p=0.722).
Cause of death distributions differed significantly across treatments in clinical trials, with most of the difference attributed to infections rather than other causes (p<0.001).
NRM estimates varied widely and were strongly influenced by follow-up duration, which was longer in trials than in real-world cohorts; median follow-up time was 18.1 versus 9.6 months, respectively.
Treatment-related differences remained consistent across sensitivity analyses relaxing follow-up restrictions and incorporating real-world studies, although follow-up time and study setting were both significant predictors of NRM.
STUDIES INCLUDED IN THE BASE CASE META-ANALYSIS
ARC-101 (anito-cel, trial, median follow-up 32.3 months, 4L or later, 32 patients, 1 NRM event, 3.1%)
iMMagine-1 (anito-cel, trial, 15.9 months, 4L or later, 117 patients, 4 NRM events, 3.4%)
CARTITUDE-2 Cohort A (cilta-cel, trial, 17.1 months, fewer than 4L, 20 patients, 2 NRM events, 10.0%)
CARTITUDE-1 (cilta-cel, trial, 18 months, 4L or later, 97 patients, 11 NRM events, 11.3%)
CARTITUDE-4 (cilta-cel, trial, 15.9 months, fewer than 4L, 208 patients, 25 NRM events, 12.0%)
CARTIFAN-1 (cilta-cel, trial, 18 months, 4L or later, 48 patients, 9 NRM events, 18.8%)
CRB-401 (ide-cel, trial, 18.1 months, 4L or later, 62 patients, 1 NRM event, 1.6%)
KarMMa-3 (ide-cel, trial, 18.6 months, fewer than 4L, 254 patients, 31 NRM events, 12.2%)
KarMMa (ide-cel, trial, 13.3 months, 4L or later, 128 patients, 16 NRM events, 12.5%)
MagnetisMM-3 Cohort A (elranatamab, trial, 14.6 months, fewer than 4L, 123 patients, 18 NRM events, 14.6%)
MajesTEC-1 (teclistamab, trial, 14.1 months, fewer than 4L, 165 patients, 19 NRM events, 11.5%)
MajesTEC-1 China cohort (teclistamab, trial, 15 months, 4L or later, 26 patients, 4 NRM events, 15.4%)
Pooled NRM point estimates with 95% confidence intervals: anito-cel 3.4% (1.4, 7.8); cilta-cel 12.6% (9.6, 16.4); ide-cel 8.8% (4.0, 18.3); elranatamab 14.6% (9.4, 22.0); teclistamab 12.0% (8.1, 17.5).
Multivariate meta-analysis odds ratios for NRM versus anito-cel reference: cilta-cel 4.42 (1.24, 15.71), p=0.0286; ide-cel 4.05 (1.13, 14.50), p=0.0363; elranatamab 5.36 (1.27, 22.56), p=0.0289; teclistamab 4.24 (1.08, 16.69), p=0.0417. Line of therapy, 4L or later versus fewer than 4L reference: 1.09 (0.63, 1.86), p=0.722.
Causes of death assessed included infections, COVID-19, cardiovascular/respiratory, organ failure, hemophagocytic lymphohistiocytosis (HLH), hemorrhage, neurotoxicity/immune effector cell-associated neurotoxicity syndrome (ICANS), cytokine release syndrome (CRS), and malignancy.
CONCLUSIONS
Anito-cel, a BCMA-targeted CAR T-cell therapy, was associated with lower observed NRM after adjustment for available study-level characteristics, relative to both other BCMA-targeting CAR T-cell and bispecific therapies.
Differences are most pronounced versus bispecific antibodies, likely driven by higher infection-related mortality in this class.
Lower observed NRM with anito-cel is consistent with a reduced infection burden, supporting a differentiated safety profile.
Limitations: These findings should be interpreted in light of the non-comparative nature of the included studies, study heterogeneity, and limited follow-up. Longer-term follow-up and real-world evidence are needed to determine whether the observed NRM advantage persists as the evidence base matures.
PLAIN LANGUAGE SUMMARY
Non-relapse mortality (NRM) measures deaths that were not caused by multiple myeloma, a type of blood cancer, getting worse. Researchers use it to help assess treatment safety.
We reviewed published research studies and studies of everyday medical practice of anito-cel and other treatments that target B-cell maturation antigen (BCMA), a protein found on myeloma cells.
Based on the available evidence, anito-cel was linked to a lower risk of NRM than the other therapies evaluated.
Overall, these findings suggest that anito-cel may be linked to fewer treatment-related deaths than similar BCMA-targeted therapies.
ABBREVIATIONS
NRM: non-relapse mortality. RRMM: relapsed/refractory multiple myeloma. LOT: line of therapy. BCMA: B-cell maturation antigen. CRS: cytokine release syndrome. HLH: hemophagocytic lymphohistiocytosis. ICANS: immune effector cell-associated neurotoxicity syndrome. CAR: chimeric antigen receptor.
KEYWORDS
non-relapse mortality, NRM, treatment-related mortality, BCMA, B-cell maturation antigen, CAR T-cell therapy, bispecific antibody, anitocabtagene autoleucel, anito-cel, ciltacabtagene autoleucel, cilta-cel, idecabtagene vicleucel, ide-cel, elranatamab, teclistamab, relapsed/refractory multiple myeloma, RRMM, systematic literature review, meta-analysis, meta-regression, safety, infection, iMMagine-1
Funded by Arcellx, Inc. and Kite, A Gilead Company. Presented at the Society of Hematologic Oncology (SOHO) Annual Meeting; September 9-12, 2026; Houston, Texas. Poster MM-744.