875 posters, 25 topics, 3,440 authors, 1,061 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
SAGES 2026 Annual Meeting Emerging Technology Session
March 25-28, 2026 | Tampa, FL, USA

P788
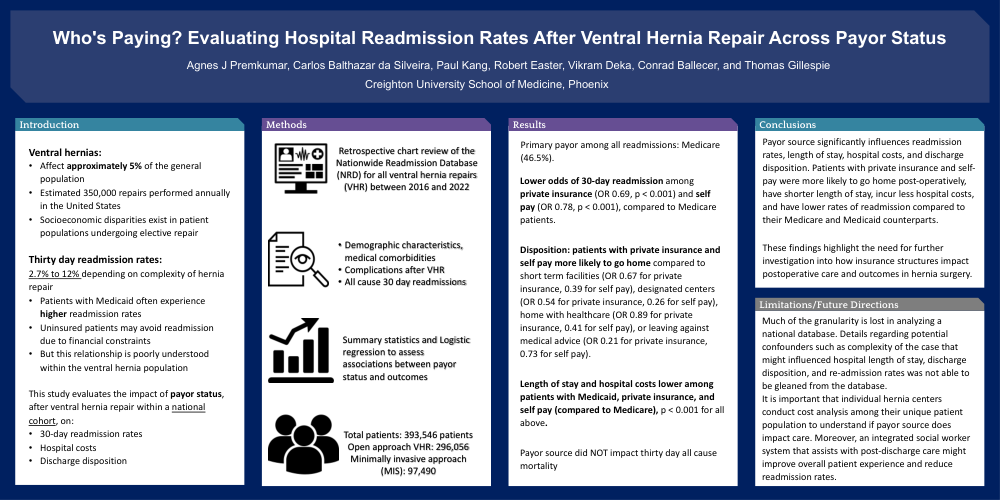
Who's Paying? Evaluating Hospital Readmission Rates After Ventral Hernia Repair Across Payor Status
Poster Presenter
Part of Topic
Quality Improvement / Health System Outcomes
Ventral hernias:
•Affect approximately 5% of the general population
•Estimated 350,000 repairs performed annually in the United States
•Socioeconomic disparities exist in patient populations undergoing elective repair
Thirty day readmission rates:
2.7% to 12% depending on complexity of hernia repair
•Patients with Medicaid often experience higher readmission rates
•Uninsured patients may avoid readmission due to financial constraints
•But this relationship is poorly understood within the ventral hernia population
This study evaluates the impact of payor status, after ventral hernia repair within a national cohort, on:
•30-day readmission rates
•Hospital costs
•Discharge disposition
Methods:
Retrospective chart review of the Nationwide Readmission Database (NRD) for all ventral hernia repairs (VHR) between 2016 and 2022, collecting demographic characteristics, medical comorbidities, complications after VHR, and all cause 30 day readmissions. Summary statistics and Logistic regression were used to assess associations between payor status and outcomes.
Results:
Primary payor among all readmissions: Medicare (46.5%). Lower odds of 30-day readmission among private insurance (OR 0.69, p < 0.001) and self pay (OR 0.78, p < 0.001), compared to Medicare patients. Disposition: patients with private insurance and self pay more likely to go home compared to short term facilities (OR 0.67 for private insurance, 0.39 for self pay), designated centers (OR 0.54 for private insurance, 0.26 for self pay), home with healthcare (OR 0.89 for private insurance, 0.41 for self pay), or leaving against medical advice (OR 0.21 for private insurance, 0.73 for self pay). Length of stay and hospital costs lower among patients with Medicaid, private insurance, and self pay (compared to Medicare), p < 0.001 for all above. Payor source did NOT impact thirty day all cause mortality.
Conclusions:
Payor source significantly influences readmission rates, length of stay, hospital costs, and discharge disposition. Patients with private insurance and self-pay were more likely to go home post-operatively, have shorter length of stay, incur less hospital costs, and have lower rates of readmission compared to their Medicare and Medicaid counterparts. These findings highlight the need for further investigation into how insurance structures impact postoperative care and outcomes in hernia surgery.
Limitations:
Much of the granularity is lost in analyzing a national database. Details regarding potential confounders such as complexity of the case that might influenced hospital length of stay, discharge disposition, and re-admission rates was not able to be gleaned from the database. It is important that individual hernia centers conduct cost analysis among their unique patient population to understand if payor source does impact care. Moreover, an integrated social worker system that assists with post-discharge care might improve overall patient experience and reduce readmission rates.