1,267 posters, 47 videos, 13 topics, 4 sessions, 853 authors
ePostersLive by SciGen Technologies S.A. All rights reserved.
SOHO 2026 Annual Meeting
September 9 - 12, 2026 | George R. Brown Convention Center, Houston, Texas

CT - 1657
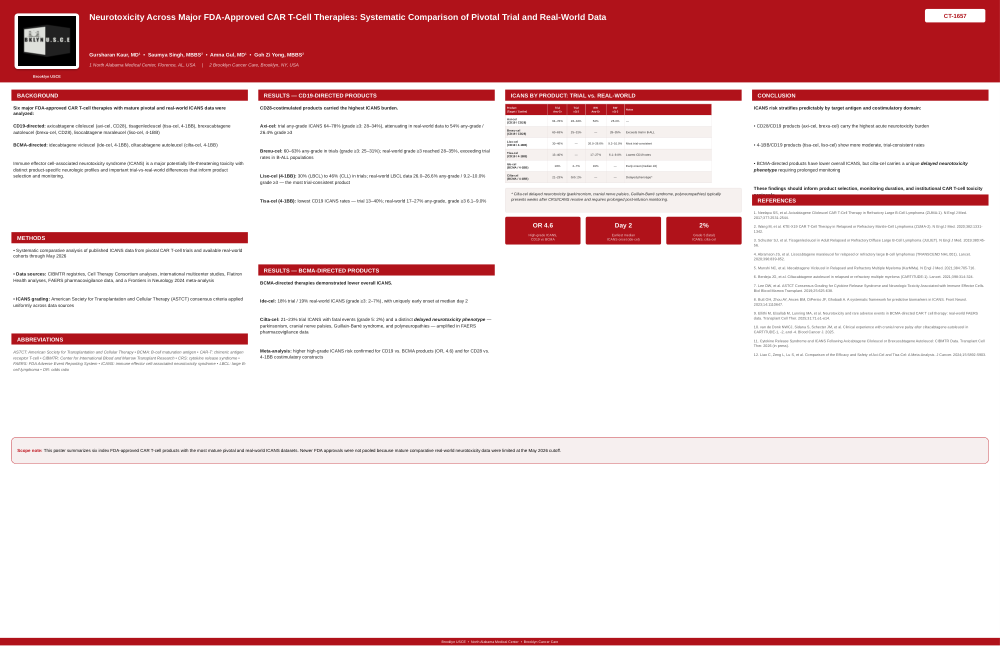
Neurotoxicity across all FDA-approved CAR-T therapies: systematic comparison of pivotal trial and real-world data
Poster Presenter
Authors
Part of Topic
Cellular Therapy (CT)
Abstract
Background: Six CAR-T cell therapies are currently FDA-approved: the CD19-directed agents axicabtagene ciloleucel (axi-cel, CD28), tisagenlecleucel (tisa-cel, 4-1BB), brexucabtagene autoleucel (brexu-cel, CD28), and lisocabtagene maraleucel (liso-cel, 4-1BB); and the BCMA-directed agents idecabtagene vicleucel (ide-cel, 4-1BB) and ciltacabtagene autoleucel (cilta-cel, 4-1BB). Immune effector cell-associated neurotoxicity syndrome (ICANS) is a major potentially life-threatening toxicity with distinct product-specific neurologic profiles and important trial-versus-real-world differences.
Methods: We performed a systematic comparative analysis of published ICANS data from pivotal CAR-T clinical trials and all available real-world cohorts through May 2026, including CIBMTR registries, Cell Therapy Consortium analyses, international multicenter studies, Flatiron Health analyses, FAERS pharmacovigilance data, and a Frontiers Neurology 2024 meta-analysis. ICANS grading followed ASTCT consensus criteria.
Results: CD19/CD28 products carried the highest ICANS burden. Axi-cel trial any-grade ICANS reached 64–78% (grade ≥3: 28–34%), attenuating in real-world data to 54% any-grade and 26.4% grade ≥3. Brexu-cel demonstrated 60–63% any-grade ICANS in trials (grade ≥3: 25–31%), while real-world grade ≥3 ICANS reached 28–35%, exceeding trial rates in B-ALL populations. CD19/4-1BB products showed lower rates: liso-cel demonstrated 30% (LBCL) to 46% (CLL) trial ICANS, with real-world LBCL data of 26–26.6% any-grade and 9.2–10% grade ≥3, representing the most trial-consistent product. Tisa-cel had the lowest CD19 ICANS rates (trial 13–40%; real-world 17–27% any-grade; grade ≥3: 6.1–9%). BCMA-directed therapies demonstrated lower ICANS overall: ide-cel showed 18% trial and 19% real-world ICANS (grade ≥3: 2–7%) with uniquely early onset at median day 2. Cilta-cel demonstrated 21–23% trial ICANS with fatal events (grade 5: 2%) and a distinct delayed neurotoxicity phenotype including parkinsonism, cranial nerve palsies, Guillain-Barré syndrome, and polyneuropathies, amplified in FAERS data. Meta-analysis confirmed higher high-grade ICANS risk with CD19 versus BCMA products (OR 4.6) and CD28 versus 4-1BB constructs.
Conclusion: ICANS risk stratifies by target antigen and costimulatory domain, with CD28/CD19 products carrying the highest acute neurotoxicity burden and cilta-cel demonstrating a unique delayed neurotoxicity phenotype requiring prolonged monitoring. These distinctions should inform product selection, monitoring duration, and institutional CAR-T protocols.
Keywords
Keywords: CAR-T therapy, ICANS, neurotoxicity, CD19, BCMA, axi-cel, cilta-cel, real-world data, cellular immunotherapy, FAERS