1,267 posters, 47 videos, 13 topics, 4 sessions, 853 authors
ePostersLive by SciGen Technologies S.A. All rights reserved.
SOHO 2026 Annual Meeting
September 9 - 12, 2026 | George R. Brown Convention Center, Houston, Texas

MPN - 1280
KRAS Mutations in Histiocytic Neoplasms: Mutation Spectrum and Response to MEK Inhibition
Part of Topic
Myeloproliferative Neoplasms (MPN)
KRAS Mutations in Histiocytic Neoplasms: Mutation Spectrum and Response to MEK Inhibition
Purpose:
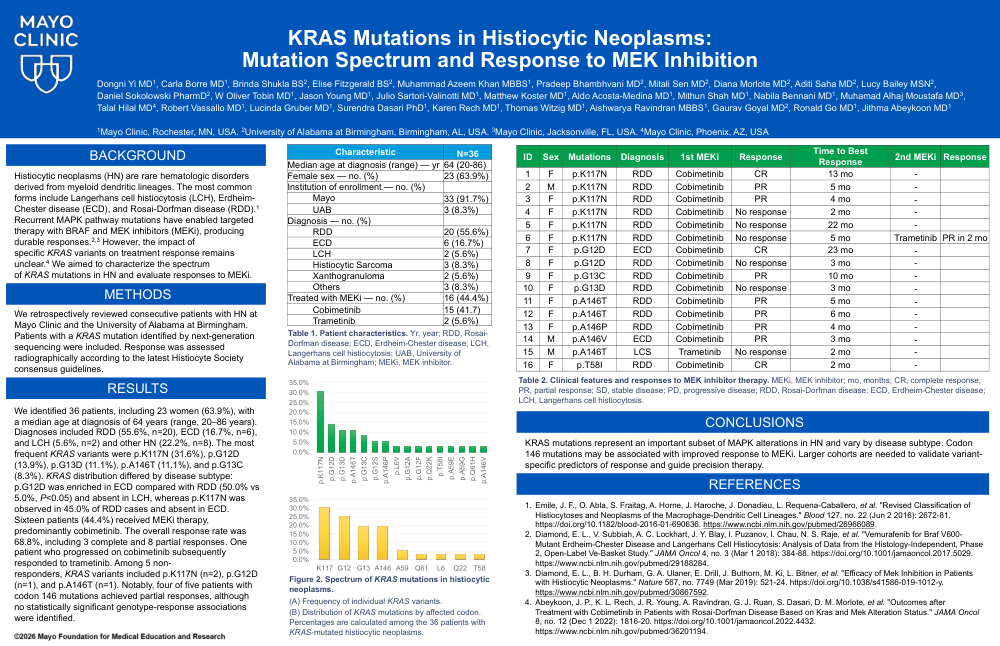
Histiocytic neoplasms (HN) are rare hematologic disorders derived from from myeloid-dendritic lineages. The most common forms include Langerhans cell histiocytosis (LCH), Erdheim-Chester disease (ECD), and Rosai-Dorfman disease (RDD). Recurrent MAPK pathway mutations have enabled targeted therapy with BRAF and MEK inhibitors (MEKi), producing durable responses. However, the impact of specific KRAS variants on treatment response remains unclear. We aimed to characterize the spectrum of KRAS mutations in HN and evaluate responses to MEKi.
Methods:
We retrospectively reviewed consecutive patients with HN at Mayo Clinic and the University of Alabama at Birmingham. Patients with a KRAS mutation identified by next-generation sequencing were included. Response was assessed radiographically according to the latest Histiocyte Society consensus guidelines.
Results:
We identified 36 patients, including 23 females (63.9%), with a median age at diagnosis of 64 years (range, 20–86). Diagnoses included RDD (55.6%, n=20), ECD (16.7%, n=6), and LCH (5.6%, n=2) and other HN (22.2%, n=8). The most frequent KRAS variants were p.K117N (31.6%), p.G12D (13.9%), p.G13D (11.1%), p.A146T (11.1%), and p.G13C (8.3%). KRAS distribution differed by disease subtype: p.G12D was enriched in ECD compared with RDD (50.0% vs 5.0%, p<0.05) and absent in LCH, whereas p.K117N was observed in 45.0% of RDD cases and absent in ECD.
Sixteen patients (44.4%) received MEKi therapy, predominantly Cobimetinib. The overall response rate was 68.8%, including 3 complete and 8 partial responses. One patient who progressed on cobimetinib subsequently responded to Trametinib. Among 5 non-responders, KRAS variants included p.K117N (n=2), p.G12D (n=1), and p.A146T (n=1). Notably, 4 of 5 patients with codon 146 mutations achieved partial responses, although no statistically significant genotype-response associations were identified.
Conclusion:
KRAS mutations represent an important subset of MAPK alterations in HN and vary by disease subtype. Codon 146 mutations may be associated with improved response to MEKi. Larger cohorts are needed to validate variant-specific predictors of response and guide precision therapy.