1,267 posters, 47 videos, 13 topics, 4 sessions, 853 authors
ePostersLive by SciGen Technologies S.A. All rights reserved.
SOHO 2026 Annual Meeting
September 9 - 12, 2026 | George R. Brown Convention Center, Houston, Texas

AML - 783
Upfront Allogeneic Stem Cell Transplantation With Individualized Venetoclax-Based Conditioning in MECOM-Rearranged Acute Myeloid Leukemia: A Single-Center Retrospective Study
Poster Presenter
Authors
Part of Topic
Acute Myeloid Leukemia (AML)
INTRODUCTION
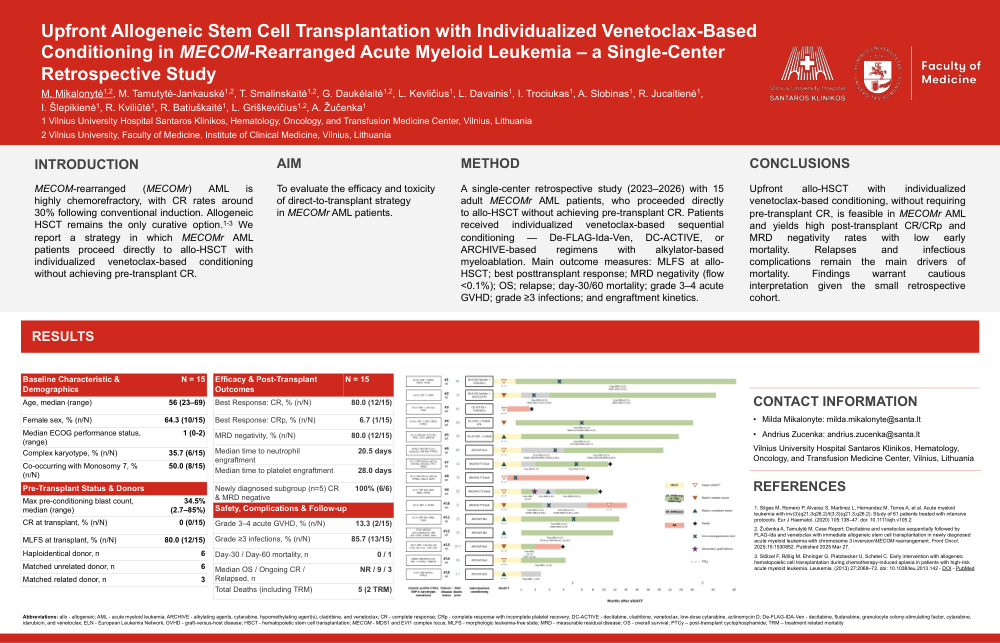
MECOM-rearranged (MECOMr) AML is highly chemorefractory, with CR rates around 30% following conventional induction. Allogeneic HSCT remains the only curative option.1-3 We report a strategy in which MECOMr AML patients proceed directly to allo-HSCT with individualized venetoclax-based conditioning without achieving pre-transplant CR.
AIM
To evaluate the efficacy and toxicity of direct-to-transplant strategy in MECOMr AML patients.
METHOD
A single-center retrospective study (2023–2026) with 15 adult MECOMr AML patients, who proceeded directly to allo-HSCT without achieving pre-transplant CR. Patients received individualized venetoclax-based sequential conditioning — De-FLAG-Ida-Ven, DC-ACTIVE, or ARCHIVE-based regimens with alkylator-based myeloablation. Main outcome measures: MLFS at allo-HSCT; best posttransplant response; MRD negativity (flow <0.1%); OS; relapse; day-30/60 mortality; grade 3–4 acute GVHD; grade ≥3 infections; and engraftment kinetics.
CONCLUSIONS
Upfront allo-HSCT with individualized venetoclax-based conditioning, without requiring pre-transplant CR, is feasible in MECOMr AML and yields high post-transplant CR/CRp and MRD negativity rates with low early mortality. Relapses and infectious complications remain the main drivers of mortality. Findings warrant cautious interpretation given the small retrospective cohort.