1,267 posters, 47 videos, 13 topics, 4 sessions, 853 authors
ePostersLive by SciGen Technologies S.A. All rights reserved.
SOHO 2026 Annual Meeting
September 9 - 12, 2026 | George R. Brown Convention Center, Houston, Texas

CT - 612
Tumor Lysis Syndrome and In-Hospital Outcomes Among Patients with Hematologic Malignancies: A National Inpatient Sample Analysis (2022)
Poster Presenter
Authors
Part of Topic
Cellular Therapy (CT)
-
Tumor lysis syndrome (TLS) is a life-threatening oncologic emergency resulting from rapid destruction of malignant cells and subsequent metabolic derangements.
-
TLS is associated with acute kidney injury, electrolyte abnormalities, cardiac arrhythmias, and multiorgan dysfunction.
-
Although the clinical manifestations of TLS are well established, contemporary national estimates evaluating its association with inpatient outcomes remain limited.
-
We evaluated the impact of TLS on mortality, organ failure, and healthcare utilization among hospitalized patients with hematologic malignancies.
-
Study Design: Retrospective cohort study using the 2022 National Inpatient Sample (NIS).
-
Study Population: Adult hospitalizations with hematologic malignancies identified using ICD-10-CM diagnosis codes.
-
Exposure: Tumor lysis syndrome identified using ICD-10-CM code E88.3 in any diagnosis position.
-
Primary Outcome: In-hospital mortality
-
Secondary Outcomes: Acute dialysis requirement, Mechanical ventilation, Length of stay (LOS)
-
Covariates: Multivariable models adjusted for Age, Sex, Race/ethnicity, Chronic kidney disease, Diabetes mellitus, Heart failure, Coronary artery disease, Hypertension, COPD, Obesity, & Liver disease
-
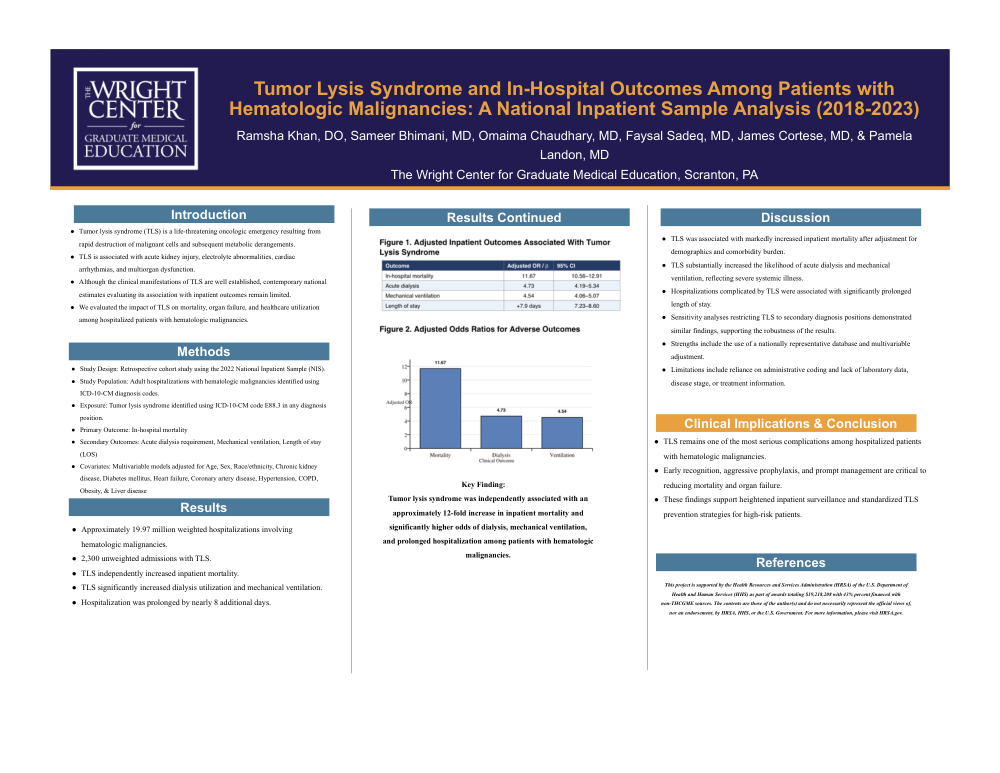
Approximately 19.97 million weighted hospitalizations involving hematologic malignancies.
-
2,300 unweighted admissions with TLS.
-
TLS independently increased inpatient mortality.
-
TLS significantly increased dialysis utilization and mechanical ventilation.
-
Hospitalization was prolonged by nearly 8 additional days.
-
TLS was associated with markedly increased inpatient mortality after adjustment for demographics and comorbidity burden.
-
TLS substantially increased the likelihood of acute dialysis and mechanical ventilation, reflecting severe systemic illness.
-
Hospitalizations complicated by TLS were associated with significantly prolonged length of stay.
-
Sensitivity analyses restricting TLS to secondary diagnosis positions demonstrated similar findings, supporting the robustness of the results.
-
Strengths include the use of a nationally representative database and multivariable adjustment.
-
Limitations include reliance on administrative coding and lack of laboratory data, disease stage, or treatment information.
-
TLS remains one of the most serious complications among hospitalized patients with hematologic malignancies.
-
Early recognition, aggressive prophylaxis, and prompt management are critical to reducing mortality and organ failure.
-
These findings support heightened inpatient surveillance and standardized TLS prevention strategies for high-risk patients.
-
-
-