1,267 posters, 47 videos, 13 topics, 4 sessions, 853 authors
ePostersLive by SciGen Technologies S.A. All rights reserved.
SOHO 2026 Annual Meeting
September 9 - 12, 2026 | George R. Brown Convention Center, Houston, Texas

CML - 602
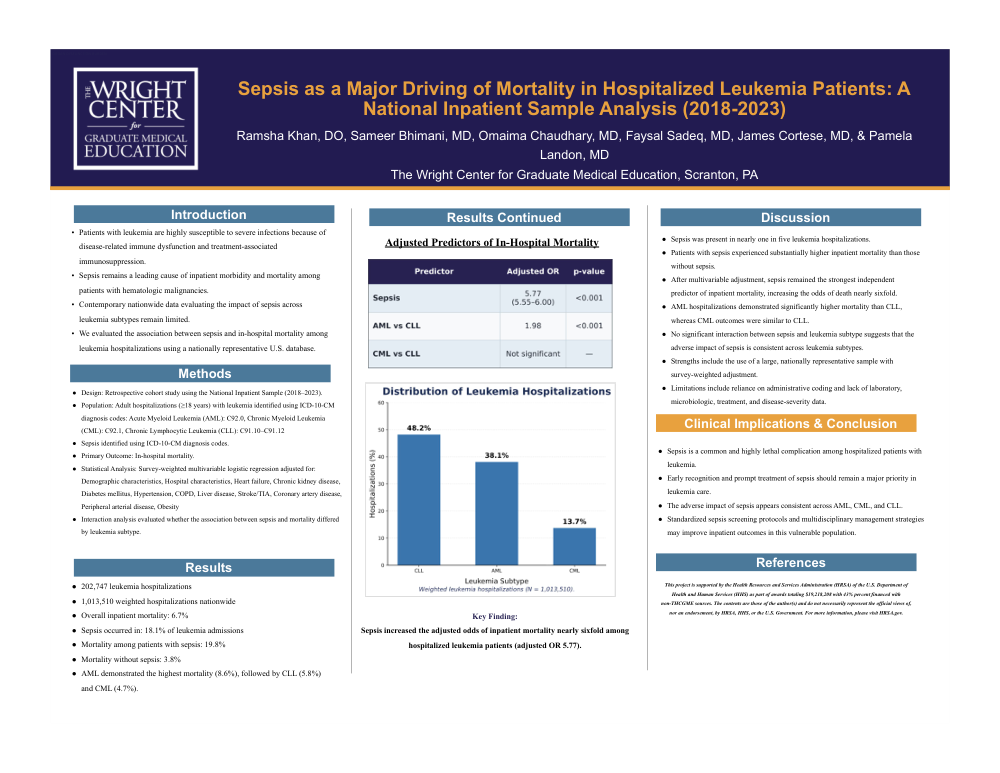
Sepsis as a Major Driver of Mortality in Hospitalized Leukemia Patients: A National Inpatient Sample Analysis (2018-2023)
Poster Presenter
Authors
Part of Topic
Chronic Myeloid Leukemia (CML)
-
Patients with leukemia are highly susceptible to severe infections because of disease-related immune dysfunction and treatment-associated immunosuppression.
-
Sepsis remains a leading cause of inpatient morbidity and mortality among patients with hematologic malignancies.
-
Contemporary nationwide data evaluating the impact of sepsis across leukemia subtypes remain limited.
-
We evaluated the association between sepsis and in-hospital mortality among leukemia hospitalizations using a nationally representative U.S. database.
-
Design: Retrospective cohort study using the National Inpatient Sample (2018–2023).
-
Population: Adult hospitalizations (≥18 years) with leukemia identified using ICD-10-CM diagnosis codes: Acute Myeloid Leukemia (AML): C92.0, Chronic Myeloid Leukemia (CML): C92.1, Chronic Lymphocytic Leukemia (CLL): C91.10–C91.12
-
Sepsis identified using ICD-10-CM diagnosis codes.
-
Primary Outcome: In-hospital mortality.
-
Statistical Analysis: Survey-weighted multivariable logistic regression adjusted for: Demographic characteristics, Hospital characteristics, Heart failure, Chronic kidney disease, Diabetes mellitus, Hypertension, COPD, Liver disease, Stroke/TIA, Coronary artery disease, Peripheral arterial disease, Obesity
-
Interaction analysis evaluated whether the association between sepsis and mortality differed by leukemia subtype.
-
202,747 leukemia hospitalizations
-
1,013,510 weighted hospitalizations nationwide
-
Overall inpatient mortality: 6.7%
-
Sepsis occurred in: 18.1% of leukemia admissions
-
Mortality among patients with sepsis: 19.8%
-
Mortality without sepsis: 3.8%
-
AML demonstrated the highest mortality (8.6%), followed by CLL (5.8%) and CML (4.7%).
-
Sepsis was present in nearly one in five leukemia hospitalizations.
-
Patients with sepsis experienced substantially higher inpatient mortality than those without sepsis.
-
After multivariable adjustment, sepsis remained the strongest independent predictor of inpatient mortality, increasing the odds of death nearly sixfold.
-
AML hospitalizations demonstrated significantly higher mortality than CLL, whereas CML outcomes were similar to CLL.
-
No significant interaction between sepsis and leukemia subtype suggests that the adverse impact of sepsis is consistent across leukemia subtypes.
-
Strengths include the use of a large, nationally representative sample with survey-weighted adjustment.
-
Limitations include reliance on administrative coding and lack of laboratory, microbiologic, treatment, and disease-severity data.
-
Sepsis is a common and highly lethal complication among hospitalized patients with leukemia.
-
Early recognition and prompt treatment of sepsis should remain a major priority in leukemia care.
-
The adverse impact of sepsis appears consistent across AML, CML, and CLL.
-
Standardized sepsis screening protocols and multidisciplinary management strategies may improve inpatient outcomes in this vulnerable population.
-
-
-