1,267 posters, 47 videos, 13 topics, 4 sessions, 853 authors
ePostersLive by SciGen Technologies S.A. All rights reserved.
SOHO 2026 Annual Meeting
September 9 - 12, 2026 | George R. Brown Convention Center, Houston, Texas

CML - 596
Predictors of In-Hospital Mortality Among Patients Hospitalized With Chronic Myeloid Leukemia: A National Inpatient Sample Analysis (2018-2023)
Poster Presenter
Authors
Part of Topic
Chronic Myeloid Leukemia (CML)
-
Chronic myeloid leukemia (CML) is a myeloproliferative neoplasm with markedly improved survival following the introduction of tyrosine kinase inhibitors.
-
Despite these advances, hospitalized patients with CML remain vulnerable to infectious complications, organ dysfunction, and multiple medical comorbidities.
-
Contemporary nationwide data identifying predictors of inpatient mortality among CML hospitalizations remain limited.
-
We evaluated demographic and clinical predictors of in-hospital mortality among hospitalized patients with CML using a nationally representative U.S. database.
Design: Retrospective cohort study using the National Inpatient Sample (2018–2023).
Population: Adult hospitalizations (≥18 years) with CML identified using ICD-10-CM diagnosis code of C92.
Primary Outcome: In-hospital mortality
Statistical Analysis: Survey-weighted multivariable logistic regression adjusted for: Demographic characteristics, Hospital characteristics, Heart failure, Chronic kidney disease, Diabetes mellitus, Hypertension, COPD, Liver disease, Stroke/TIA, Coronary artery disease, Peripheral arterial disease, Obesity
-
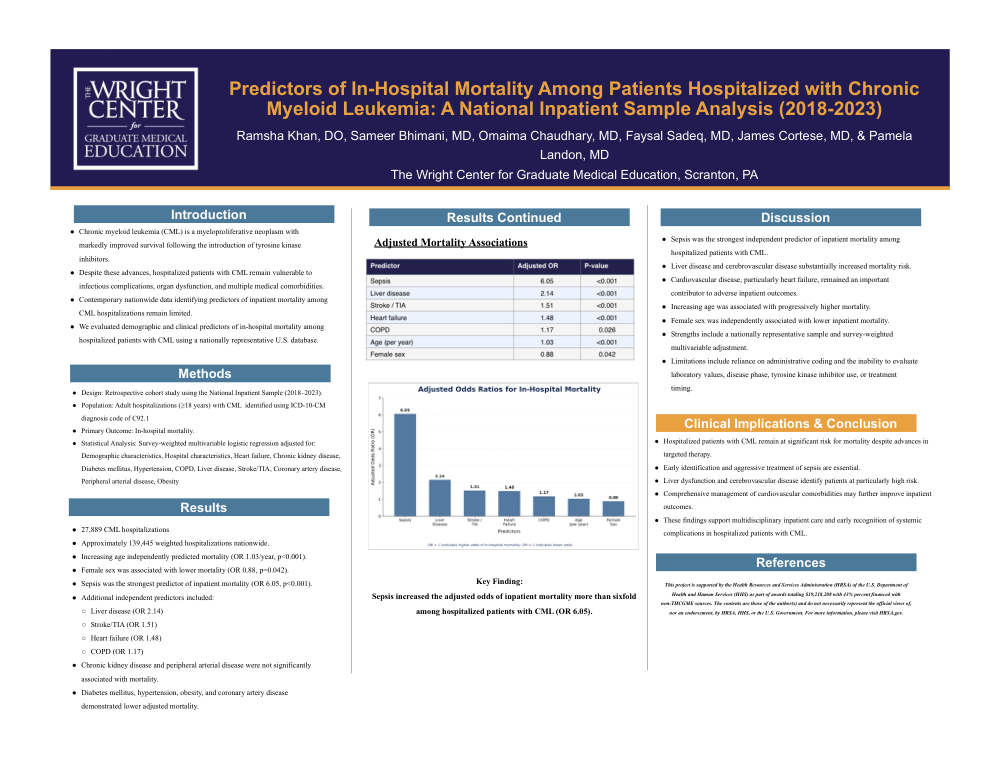
27,889 CML hospitalizations
-
Approximately 139,445 weighted hospitalizations nationwide.
-
Increasing age independently predicted mortality (OR 1.03/year, p<0.001).
-
Female sex was associated with lower mortality (OR 0.88, p=0.042).
-
Sepsis was the strongest predictor of inpatient mortality (OR 6.05, p<0.001).
-
Additional independent predictors included:
-
Liver disease (OR 2.14)
-
Stroke/TIA (OR 1.51)
-
Heart failure (OR 1.48)
-
COPD (OR 1.17)
-
Chronic kidney disease and peripheral arterial disease were not significantly associated with mortality.
-
Diabetes mellitus, hypertension, obesity, and coronary artery disease demonstrated lower adjusted mortality.
-
Sepsis was the strongest independent predictor of inpatient mortality among hospitalized patients with CML.
-
Liver disease and cerebrovascular disease substantially increased mortality risk.
-
Cardiovascular disease, particularly heart failure, remained an important contributor to adverse inpatient outcomes.
-
Increasing age was associated with progressively higher mortality.
-
Female sex was independently associated with lower inpatient mortality.
-
Strengths include a nationally representative sample and survey-weighted multivariable adjustment.
-
Limitations include reliance on administrative coding and the inability to evaluate laboratory values, disease phase, tyrosine kinase inhibitor use, or treatment timing.
-
Hospitalized patients with CML remain at significant risk for mortality despite advances in targeted therapy.
-
Early identification and aggressive treatment of sepsis are essential.
-
Liver dysfunction and cerebrovascular disease identify patients at particularly high risk.
-
Comprehensive management of cardiovascular comorbidities may further improve inpatient outcomes.
-
These findings support multidisciplinary inpatient care and early recognition of systemic complications in hospitalized patients with CML.
-
-
-