516 posters, 59 topics, 63 sessions, 1,127 authors, 353 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
2026 SOAP Annual Meeting
April 29 - May 3, 2026 | Montreal, Quebec Canada

2337456
A Case Report of Takotsubo Cardiomyopathy in Pregnancy: When Form Reflects Dysfunction
Poster Presenter
Authors
Affiliations
Part of Topic
Potpourri
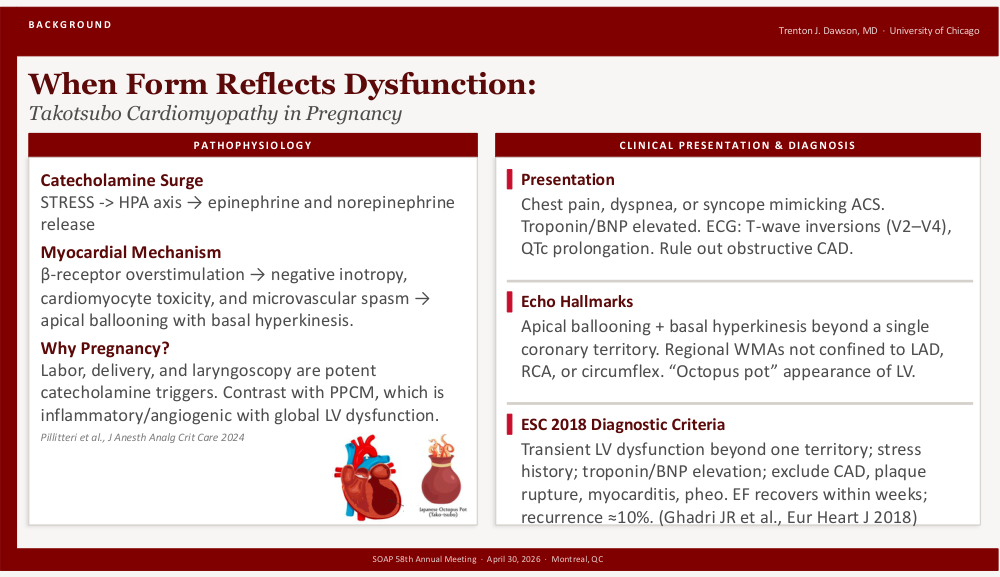
When Form Reflects Dysfunction:
Takotsubo Cardiomyopathy in Pregnancy
PATHOPHYSIOLOGY
Catecholamine Surge
STRESS -> HPA axis → epinephrine and norepinephrine release
Myocardial Mechanism
B-receptor overstimulation → negative inotropy, cardiomyocyte toxicity, and microvascular spasm → apical ballooning with basal hyperkinesis.
Why Pregnancy?
Labor, delivery, and laryngoscopy are potent catecholamine triggers. Contrast with PPCM, which is inflammatory/angiogenic with global LV dysfunction.
Pillitteri et al., J Anesth Analg Crit Care 2024
CLINICAL PRESENTATION & DIAGNOSIS
Presentation
Chest pain, dyspnea, or syncope mimicking ACS.
Troponin/BNP elevated. ECG: T-wave inversions (V2-V4),
QTc prolongation. Rule out obstructive CAD.
Echo Hallmarks
Apical ballooning + basal hyperkinesis beyond a single coronary territory. Regional WMAs not confined to LAD, RCA, or circumflex. "Octopus pot" appearance of LV.
1 ESC 2018 Diagnostic Criteria
Transient LV dysfunction beyond one territory; stress history; troponin/BNP elevation; exclude CAD, plaque rupture, myocarditis, pheo. EF recovers within weeks; recurrence ≥10%. (Ghadri JR et al., Eur Heart J 2018)
Case of Recurrent Intrapartum TCM
PRESENTATION, WORKUP & MANAGEMENT
Patient
33 y/o G5P3013, 38w0d. Prior postpartum TCM (2020, EF nadir 45%).
PMH: obesity, OSA, GERD. PSH: cesarean x2. Acute chest pain and dyspnea. Anxious, diaphoretic. BP 123/71, HR 78, Sp0,99%
I Workup
Trop T 390 (nl <147), BNP 221 (nl <125). ECG: T-wave inversions V2-V4, no ST changes. POCUS → TTE confirmed EF 45-47%, apical hypokinesis.
CT coronary: no CAD.
Anesthesia & Delivery
CSE with slow epidural titration to T4. Phenylephrine infusion. Healthy neonate. Serial POCUS confirmed stable apical ballooning throughout, no LVOT obstruction. QBL 975 mL (atony - oxytocin + massage). 1.5L LR.
Recovery & Follow-Up
Post-op hypotension (POCUS: hypovolemic) → fluids.
Telemetry x72h. Discharged POD4. TTE at 8 weeks: EF 51-
61%, wall motion normalized.
POCUS FINDINGS - INTRAPARTUM
Apical 4-Chamber • apical ballooning, basal hyperkinesis
Parasternal Short-Axis • elliptical LV, anterolateral hypokinesis
Key Teaching Points
|
|
POCUS Drives Diagnosis |
|
Neuraxial Anesthesia is Preferred |
|
Phenylephrine is First-Line |
|
01 |
Bedside POCUS showing apical ballooning and basal hyperkinesis prompted the diagnosis prior to formal TTE. Anesthesiologists proficient in POCUS can identify morphology in real time. Obstetric Drug Selection Oxytocin: Carboprost: Methergine: Terbutaline: Nitroglycerin: |
02 |
CSE with slow, incremental epidural dosing. Minimize abrupt afterload reduction. Avoid sympathetic surge from inadequate analgesia or laryngoscopy. |
03 |
Pure a-agonism restores afterload without raising HR or contractility. Avoid ephedrine, dopamine, dobutamine — catecholamine excess worsens the underlying B-receptor overstimulation. (Ghadri JR et al., Eur Heart J 2018) |
|
|
|
06 |
Prognosis is Favorable; Follow-Up Matters |
||
|
04 |
05 |
Multidisciplinary Planning is Essential |
LV function typically recovers within 4-8 weeks. Recurrence =10%. Arrange cardiology follow-up, remote BP monitoring, and counsel on recurrence risk (Lyon et al., JACC 2021) |