516 posters, 59 topics, 63 sessions, 1,127 authors, 353 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
2026 SOAP Annual Meeting
April 29 - May 3, 2026 | Montreal, Quebec Canada

2341663
Anesthetic Management of Cesarean Delivery in a Parturient with Congenital Long QT Syndrome and an Implantable Cardioverter-Defibrillator
Poster Presenter
Authors
Affiliations
null,
Part of Topic
ARRHYTHMIAS, AICDS, AND PACEMAKERS
Anesthetic Management of Cesarean Delivery in a Parturient with Congenital Long QT Syndrome and an Implantable Cardioverter-Defibrillator
Background
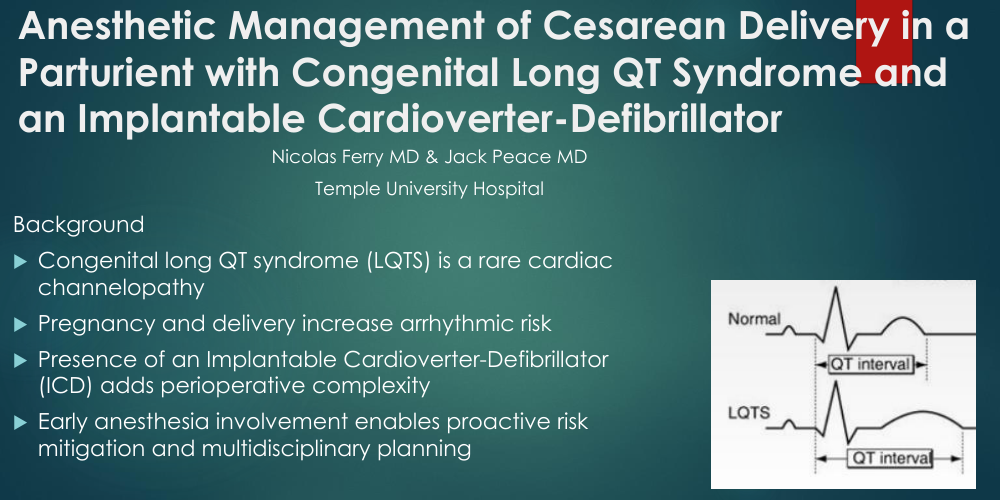
uCongenital long QT syndrome (LQTS) is a rare cardiac channelopathy
uPregnancy and delivery increase arrhythmic risk
uPresence of an Implantable Cardioverter-Defibrillator (ICD) adds perioperative complexity
uEarly anesthesia involvement enables proactive risk mitigation and multidisciplinary planning
Case
uPatient
u42-year-old G3P1 with congenital Long QT Syndrome
uPrior ventricular fibrillation arrest → ICD
uIntermittent beta-blocker adherence; QTc 434-448 ms
uPerioperative Management
uAdmission to telemetry with aggressive repletion
uMultidisciplinary care
uICD interrogation
uAnesthetic Plan
uCesarean delivery with CSE technique
uAvoided QT-prolonging medications
uPhenylephrine for hemodynamic support
uPreemptive, aggressive analgesia
uOutcome
uUncomplicated cesarean delivery
uNo perioperative arrhythmias
uPostpartum Course
uEnvironmental safeguards
uAbdominal pain → aggressive analgesia (improved by POD2)
uContinued electrolyte repletion
uPOD2 headache → conservative management
Teaching
uCongenital Long QT Syndrome requires strict avoidance of QT-prolonging medications
uElectrolyte optimization is critical throughout the peri- and postpartum period
uNeuraxial anesthesia with avoidance of epinephrine to minimize sympathetic stimulation
uPhenylephrine preferred over ephedrine in LQTS patients
uPerioperative management of Implantable Cardioverter-Defibrillator (ICD) is essential
uPeri/Postoperative pain and physiologic stress increases arrhythmic risk → aggressive analgesia is key
uMultidisciplinary coordination = better outcomes in high-risk cardiac parturients
uSystem-level safeguards (equipment readiness, visual reminders) reduce risk of medication and response errors