516 posters, 59 topics, 63 sessions, 1,127 authors, 353 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
2026 SOAP Annual Meeting
April 29 - May 3, 2026 | Montreal, Quebec Canada

2338708
Second Trimester Abortion Complicated by Atypical Hemolytic Uremic Syndrome
Poster Presenter
Authors
Affiliations
Part of Topic
Misc Hematology
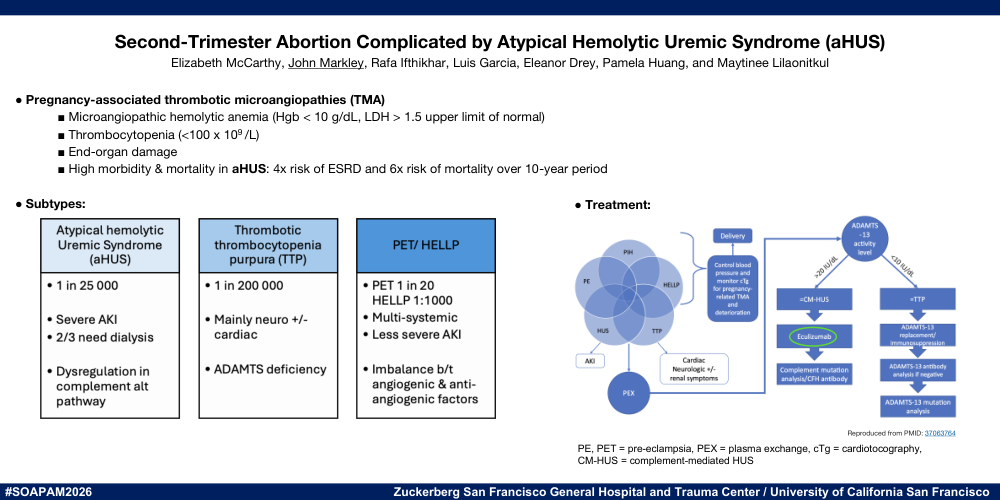
Second-Trimester Abortion Complicated by Atypical Hemolytic Uremic Syndrome (aHUS)
Elizabeth McCarthy, John Markley, Rafa Ifthikhar, Luis Garcia, Eleanor Drey, Pamela Huang, and Maytinee Lilaonitkul
●Pregnancy-associated thrombotic microangiopathies (TMA)
■Microangiopathic hemolytic anemia (Hgb < 10 g/dL, LDH > 1.5 upper limit of normal)
■Thrombocytopenia (<100 x 109 /L)
■End-organ damage
■High morbidity & mortality in aHUS: 4x risk of ESRD and 6x risk of mortality over 10-year period
●Subtypes:
●Case
○24-year-old woman presented for 24-week dilation and evacuation for undesired pregnancy
●Intraop course
○Anesthesia: Deep sedation with paracervical block
○Complicated by post-abortion hemorrhage (EBL 1.7 L) and DIC (Hgb 6.4 g/dL, Plt 89 K/mL, INR 1.7, Fib 65 mg/dL)
○Management
■Intrauterine balloon
■Transfusion: 4 U pRBC, 6 U FFP, 1 U platelet, 5 g fibrinogen concentrate
■Bilateral uterine artery embolization
●ICU postop course
○Rapidly progressive AKI
■Serum creatinine 0.73 mg/dL (pre-op) → 7.62 mg/dL (peak POD4)
○Hematology/nephrology consultations
○DDx: ATN, contrast nephropathy, TMA
○TMA workup
■HELLP, TTP, APLS ruled out
■aHUS
●Equivocal complement genetic panel
●Elevated soluble complement 5b-9 (332 ng/mL)
●Outcome
○Transferred to tertiary care center to initiate eculizumab (complement C5 inhibitor)
○Self-directed discharge before treatment started
○Re-presented on POD11 for SOB
■Diagnosed with new heart failure with mildly reduced ejection fraction (EF 40-45%). DDx peripartum- versus TMA/aHUS-associated cardiomyopathy → started on guideline-directed medical therapy
■Serum creatinine 1.99 g/dL → deferred eculizumab after risk and benefits discussion
●Teaching Points
○aHUS
■Diagnostic challenge due to clinical overlap with other pregnancy-associated TMAs
■Medical emergency with high risk of rapid progression to ESRD
■Early involvement of multidisciplinary specialists
■Prompt treatment with eculizumab improves renal outcomes
○Eculizumab
■Complement (C5) inhibitor
■Appears safe in pregnancy (limited data)
■Plasma exchange if complement inhibitor therapy unavailable
○Optimal management of subsequent pregnancies remains unknown
■Increased risk of recurrence of aHUS or PET
■C5 inhibitor prophylaxis may be warranted in high-risk cases
References:
1.PMID: 22270271
2.PMID: 39156777
3.PMID: 41477157
4.PMID: 28101432