516 posters, 59 topics, 63 sessions, 1,127 authors, 353 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
2026 SOAP Annual Meeting
April 29 - May 3, 2026 | Montreal, Quebec Canada

2320992
Peripartum Management of Carbamoyl Phosphate Synthetase I Deficiency: A Case Across Two Pregnancies
Poster Presenter
Part of Topic
Pharmacology Challenges
Peripartum Management of Carbamoyl Phosphate Synthetase I Deficiency:
A Case Across Two Pregnancies
Antanina Voit MD (voit03@osumc.edu), Goran Ristev MD, Yun Xia MD, Teri Gray MD
Department of Anesthesiology, The Ohio State University Wexner Medical Center, Columbus, OH
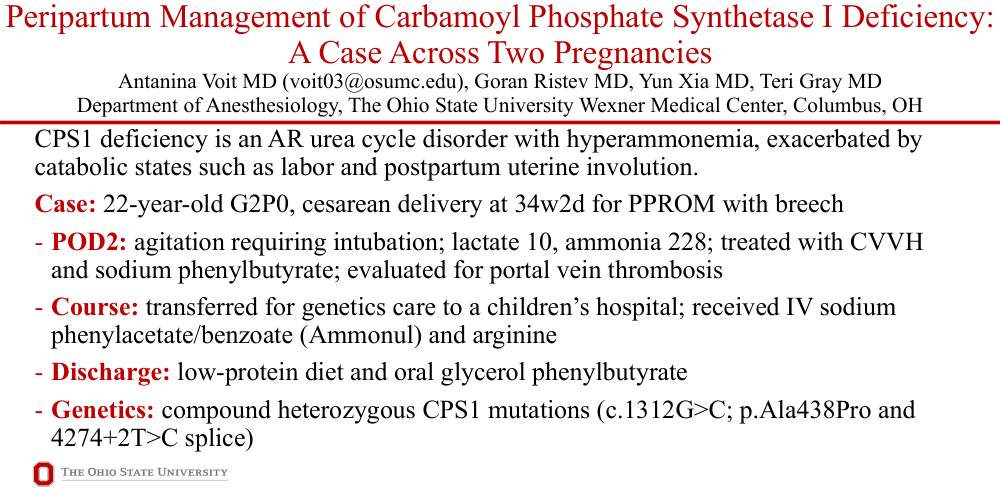
CPS1 deficiency is an AR urea cycle disorder with hyperammonemia, exacerbated by
catabolic states such as labor and postpartum uterine involution.
Case: 22-year-old G2P0, cesarean delivery at 34w2d for PPROM with breech
- POD2: agitation requiring intubation; lactate 10, ammonia 228; treated with CVVH
and sodium phenylbutyrate; evaluated for portal vein thrombosis
- Course: transferred for genetics care to a children’s hospital; received IV sodium
phenylacetate/benzoate (Ammonul) and arginine
- Discharge: low-protein diet and oral glycerol phenylbutyrate
- Genetics: compound heterozygous CPS1 mutations (c.1312G>C; p.Ala438Pro and
4274+2T>C splice)
Pregnancy 2 (Age 30):
- 37w3d induction, TOLAC; pregnancy complicated by IUGR
- Baseline ammonia 60 µmol/L; stable (60 - 80) during labor with
epidural
- Repeat C-section for NRFHT; intraoperative hemorrhage requiring transfusion
Postpartum Course:
- Ammonia peak 160 µmol/L
- Treated with D10 infusion + 20% Intralipid (2 g/kg) for 24h to promote anabolism. Ammonia improved to 79 µmol/L.
- POD2 fever, treated as endometritis (clindamycin/gentamicin)
- ED presentation 2 weeks postpartum: lethargy with ammonia 78 µmol/L, improved with hydration.
- Outcome:
- Ammonia 77 - 148 µmol/L postpartum; neurologically intact
- Discharged POD4 with ammonia 80 µmol/L on oral therapyPregnancy can unmask urea cycle disorders; presentations include encephalopathy, psychosis, hallucinations, vomiting, abdominal pain. Trend ammonia frequently
Management:
- Maintain anabolic state with IV D10 and 20% Intralipid (2 g/kg)
- Continue and implement nitrogen scavengers
Risk Factors for Hyperammonemia:
- Labor with intense muscle activity, poor oral intake
- Postpartum uterine involution with increased amino acid load
- Infection, surgery, pain, sleep deprivation
- Steroids, transfusions, albumin due to increased catabolism or protein load
- breastfeeding increases energy demand (approximately 500 kcal/day); involve a dietician
References:
Murphey K, Krishna I, Li H. Inborn errors of metabolism and pregnancy. Am J Obstet Gynecol MFM. 2024;6(8):101399. doi:10.1016/j.ajogmf.2024.101399.
Nitzahn M, Lipshutz GS. CPS1: Looking at an ancient enzyme in a modern light. Mol Genet Metab. 2020;131(3):289–298. doi:10.1016/j.ymgme.2020.10.003.