875 posters, 25 topics, 3,440 authors, 1,061 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
SAGES 2026 Annual Meeting Emerging Technology Session
March 25-28, 2026 | Tampa, FL, USA

P067
Comparison of Surgical Outcomes Between Laparoscopic eTEP, Open Rives-Stoppa, and Lichtenstein's Hernioplasty for Bilateral Inguinal Hernia
Poster Presenter
Authors
Affiliations
Part of Topic
Abdominal Wall Hernias
Introduction
Bilateral inguinal hernia repair remains a common surgical challenge. The goals of treatment are durable repair, low recurrence, reduced postoperative pain, early recovery, and minimal chronic groin discomfort. Open Lichtenstein repair remains widely practiced because of its technical familiarity and reproducibility. However, posterior plane approaches such as Stoppa repair and minimally invasive extraperitoneal techniques such as eTEP may offer advantages in bilateral disease by allowing wide preperitoneal mesh coverage while potentially reducing nerve-related chronic pain.
The present study compares short-term outcomes among eTEP, open Stoppa repair, and open Lichtenstein hernioplasty in patients undergoing surgery for bilateral inguinal hernia.
Materials and Methods
Study design
Retrospective comparative study.
Study population
A total of 661 patients with bilateral inguinal hernia were included:
- eTEP: 87 patients
- Stoppa: 113 patients
- Open Lichtenstein: 461 patients
Outcomes
The following outcomes were analyzed:
- Postoperative visual analogue score (VAS)
- Mean operative time
- Length of hospital stay
- Postoperative seroma
- Recurrence at 6 months
- Inguinodynia at 6 months
- Mesh infection
Statistical analysis
Continuous variables were reported as means because measures of spread were unavailable. Therefore, no formal significance testing could be performed for VAS, operative time, or hospital stay.
Categorical variables were expressed as frequency and percentage. Overall group comparison was performed using chi-square testing. Pairwise comparisons were assessed with Fisher’s exact test because of low event counts in several cells. A two-sided p < 0.05 was considered statistically significant.
Results
Table 1. Descriptive outcomes
|
Outcome |
eTEP (n=87) |
Stoppa (n=113) |
Open Lichtenstein (n=461) |
|
Postoperative VAS |
2.0 |
2.5 |
4.0 |
|
Mean operative time (min) |
76 |
61 |
90 |
|
Mean hospital stay (days) |
2.0 |
3.0 |
3.5 |
|
Seroma, n (%) |
7 (8.0%) |
3 (2.7%) |
17 (3.7%) |
|
Recurrence at 6 months, n (%) |
1 (1.1%) |
1 (0.9%) |
7 (1.5%) |
|
Inguinodynia, n (%) |
1 (1.1%) |
0 (0.0%) |
37 (8.0%) |
|
Mesh infection, n (%) |
0 (0.0%) |
0 (0.0%) |
3 (0.7%) |
Categorical outcome comparisons
Seroma
Seroma developed in 7/87 (8.0%) patients in the eTEP group, 3/113 (2.7%) in the Stoppa group, and 17/461 (3.7%) in the open Lichtenstein group. The overall difference was not statistically significant (chi-square p=0.119).
Pairwise Fisher testing
- eTEP vs Stoppa: p=0.106
- eTEP vs Lichtenstein: p=0.084
- Stoppa vs Lichtenstein: p=0.778
Interpretation: eTEP showed a numerically higher seroma rate, but the dataset does not provide sufficient evidence that the groups differ statistically.
Recurrence at 6 months
Recurrence rates were low in all groups:
- eTEP: 1/87 (1.1%)
- Stoppa: 1/113 (0.9%)
- Open Lichtenstein: 7/461 (1.5%)
The overall difference was not significant (p=0.859). Pairwise comparisons were also non-significant.
Interpretation: Based on 6-month data alone, the three techniques appear similar with respect to early recurrence.
Inguinodynia
Inguinodynia occurred in:
- eTEP: 1/87 (1.1%)
- Stoppa: 0/113 (0.0%)
- Open Lichtenstein: 37/461 (8.0%)
This was the only outcome with a strong statistically significant overall difference (p=0.00064)
Pairwise Fisher testing:
- eTEP vs Stoppa: p=0.435
- eTEP vs Lichtenstein: p=0.019
- Stoppa vs Lichtenstein: p=0.00038
Interpretation: both posterior-plane approaches, especially Stoppa, were associated with much lower chronic groin pain than open Lichtenstein repair.
Mesh infection
Mesh infection was rare
- eTEP: 0/87
- Stoppa: 0/113
- Open Lichtenstein: 3/461 (0.7%)
Overall comparison was not significant (p=0.520).
Interpretation: mesh infection was uncommon in all three groups.
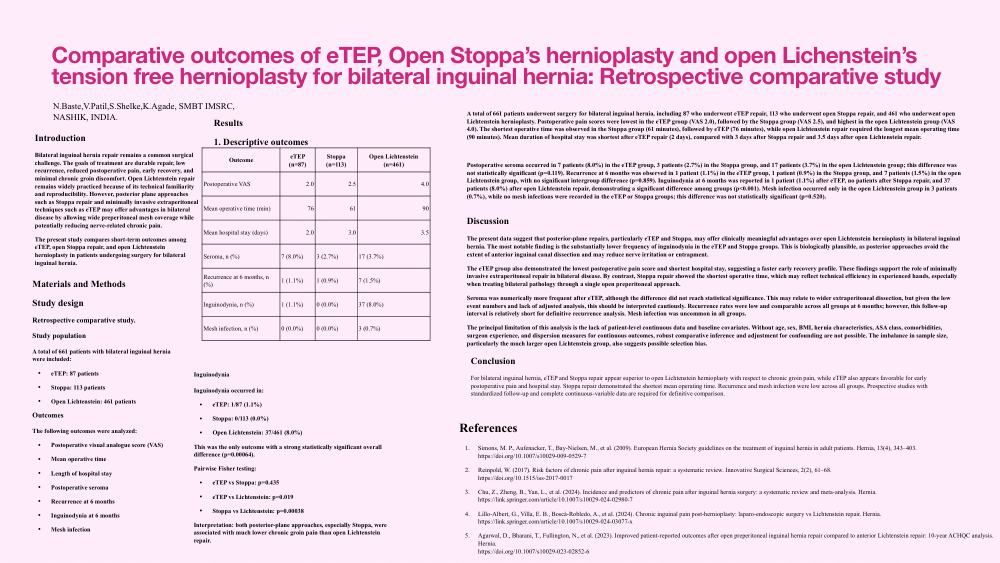
A total of 661 patients underwent surgery for bilateral inguinal hernia, including 87 who underwent eTEP repair, 113 who underwent open Stoppa repair, and 461 who underwent open Lichtenstein hernioplasty. Postoperative pain scores were lowest in the eTEP group (VAS 2.0), followed by the Stoppa group (VAS 2.5), and highest in the open Lichtenstein group (VAS 4.0). The shortest operative time was observed in the Stoppa group (61 minutes), followed by eTEP (76 minutes), while open Lichtenstein repair required the longest mean operating time (90 minutes). Mean duration of hospital stay was shortest after eTEP repair (2 days), compared with 3 days after Stoppa repair and 3.5 days after open Lichtenstein repair.
Postoperative seroma occurred in 7 patients (8.0%) in the eTEP group, 3 patients (2.7%) in the Stoppa group, and 17 patients (3.7%) in the open Lichtenstein group; this difference was not statistically significant (p=0.119). Recurrence at 6 months was observed in 1 patient (1.1%) in the eTEP group, 1 patient (0.9%) in the Stoppa group, and 7 patients (1.5%) in the open Lichtenstein group, with no significant intergroup difference (p=0.859). Inguinodynia at 6 months was reported in 1 patient (1.1%) after eTEP, no patients after Stoppa repair, and 37 patients (8.0%) after open Lichtenstein repair, demonstrating a significant difference among groups (p<0.001). Mesh infection occurred only in the open Lichtenstein group in 3 patients (0.7%), while no mesh infections were recorded in the eTEP or Stoppa groups; this difference was not statistically significant (p=0.520).
Discussion
The present data suggest that posterior-plane repairs, particularly eTEP and Stoppa, may offer clinically meaningful advantages over open Lichtenstein hernioplasty in bilateral inguinal hernia. The most notable finding is the substantially lower frequency of inguinodynia in the eTEP and Stoppa groups. This is biologically plausible, as posterior approaches avoid the extent of anterior inguinal canal dissection and may reduce nerve irritation or entrapment.
The eTEP group also demonstrated the lowest postoperative pain score and shortest hospital stay, suggesting a faster early recovery profile. These findings support the role of minimally invasive extraperitoneal repair in bilateral disease. By contrast, Stoppa repair showed the shortest operative time, which may reflect technical efficiency in experienced hands, especially when treating bilateral pathology through a single open preperitoneal approach.
Seroma was numerically more frequent after eTEP, although the difference did not reach statistical significance. This may relate to wider extraperitoneal dissection, but given the low event numbers and lack of adjusted analysis, this should be interpreted cautiously. Recurrence rates were low and comparable across all groups at 6 months; however, this follow-up interval is relatively short for definitive recurrence analysis. Mesh infection was uncommon in all groups.
The principal limitation of this analysis is the lack of patient-level continuous data and baseline covariates. Without age, sex, BMI, hernia characteristics, ASA class, comorbidities, surgeon experience, and dispersion measures for continuous outcomes, robust comparative inference and adjustment for confounding are not possible. The imbalance in sample size, particularly the much larger open Lichtenstein group, also suggests possible selection bias.
Conclusion
For bilateral inguinal hernia, eTEP and Stoppa repair appear superior to open Lichtenstein hernioplasty with respect to chronic groin pain, while eTEP also appears favorable for early postoperative pain and hospital stay. Stoppa repair demonstrated the shortest mean operating time. Recurrence and mesh infection were low across all groups. Prospective studies with standardized follow-up and complete continuous-variable data are required for definitive comparison.
References
- Simons, M. P., Aufenacker, T., Bay-Nielsen, M., et al. (2009). European Hernia Society guidelines on the treatment of inguinal hernia in adult patients. Hernia, 13(4), 343–403.
https://doi.org/10.1007/s10029-009-0529-7 - Reinpold, W. (2017). Risk factors of chronic pain after inguinal hernia repair: a systematic review. Innovative Surgical Sciences, 2(2), 61–68.
https://doi.org/10.1515/iss-2017-0017 - Chu, Z., Zheng, B., Yan, L., et al. (2024). Incidence and predictors of chronic pain after inguinal hernia surgery: a systematic review and meta-analysis. Hernia.
https://link.springer.com/article/10.1007/s10029-024-02980-7 - Lillo-Albert, G., Villa, E. B., Boscà-Robledo, A., et al. (2024). Chronic inguinal pain post-hernioplasty: laparo-endoscopic surgery vs Lichtenstein repair. Hernia.
https://link.springer.com/article/10.1007/s10029-024-03077-x - Agarwal, D., Bharani, T., Fullington, N., et al. (2023). Improved patient-reported outcomes after open preperitoneal inguinal hernia repair compared to anterior Lichtenstein repair: 10-year ACHQC analysis. Hernia.
https://doi.org/10.1007/s10029-023-02852-6 - Malazgirt, Z., Ozkan, K., Dervisoglu, A., & Kaya, E. (2000). Comparison of Stoppa and Lichtenstein techniques in the repair of bilateral inguinal hernias. Hernia, 4, 282–285.
https://doi.org/10.1007/BF01201080 - Pisanu, A., Podda, M., Saba, A., Porceddu, G., & Uccheddu, A. (2015). Meta-analysis and review of prospective randomized trials comparing laparoscopic and Lichtenstein techniques in recurrent inguinal hernia repair. Hernia, 19, 355–366.
https://doi.org/10.1007/s10029-014-1281-1 - Hajibandeh, S., Hajibandeh, S., Evans, L. A., & Havard, T. J. (2022). Meta-analysis of the outcomes of trans-rectus sheath extra-peritoneal procedure (TREPP) for inguinal hernia. Hernia, 26, 449–460.
https://doi.org/10.1007/s10029-021-02554-x - Yilmaz, A. H., & Ulutas, M. E. (2025). Comparative study of the enhanced-view totally extraperitoneal technique versus traditional TEP technique in recurrent inguinal hernia repair. BMC Surgery.
https://doi.org/10.1186/s12893-025-03105-2 - Melkemichel, M., Holmberg, H., & Dahlstrand, U. (2025). Short- and long-term outcomes after groin hernia surgery: population-based study from the Swedish Hernia Register. Journal of Clinical Medicine.
https://www.mdpi.com/2077-0383/14/7/2397 - Zwaans, W. A. R. (2017). Strategies for chronic inguinal pain after hernia surgery. Maastricht University.
https://cris.maastrichtuniversity.nl/files/16805490/a5826.pdf - Matikainen, M. (2022). Acute and chronic pain after inguinal hernia surgery. University of Eastern Finland.
https://erepo.uef.fi/bitstreams/612d81b6-b864-49bb-b09a-6b720b34b56e/download