875 posters, 25 topics, 3,440 authors, 1,061 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
SAGES 2026 Annual Meeting Emerging Technology Session
March 25-28, 2026 | Tampa, FL, USA

P035
Parachute technique for placement of sublay intraperitoneal mesh for umbilical hernia with abdominoplasty
Poster Presenter
Authors
Fadi Jallad, Abdulrahman Al -sahby, Jareer Hemidan, Mohammad Qudaih, Mohammed Manhal
Affiliations
Part of Topic
Abdominal Wall Hernias
Parachute technique for placement of sublay intraperitoneal mesh for umbilical hernia with abdominoplasty
Fadi Jallad, Jareer Hemidan,Abdulrahman ALSahaby, M. Qudaih, M. Manhal
Introduction
Umbilical hernia is a common finding during abdominoplasty surgeries. Repairing the umbilical hernia with intraperitoneal sublay mesh has a low recurrence rate.
Technique Description:
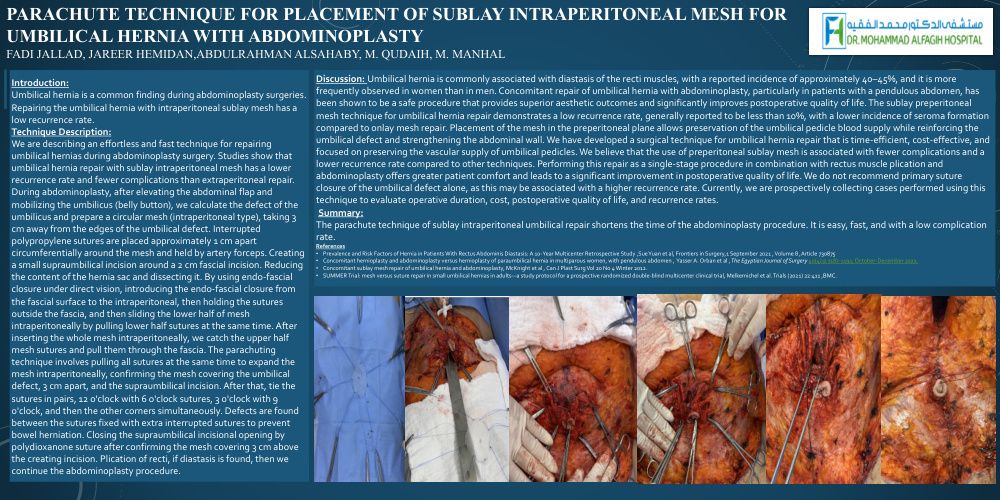
We are describing an effortless and fast technique for repairing umbilical hernias during abdominoplasty surgery. Studies show that umbilical hernia repair with sublay intraperitoneal mesh has a lower recurrence rate and fewer complications than extraperitoneal repair. During abdominoplasty, after elevating the abdominal flap and mobilizing the umbilicus (belly button), we calculate the defect of the umbilicus and prepare a circular mesh (intraperitoneal type), taking 3 cm away from the edges of the umbilical defect. Interrupted polypropylene sutures are placed approximately 1 cm apart circumferentially around the mesh and held by artery forceps. Creating a small supraumbilical incision around a 2 cm fascial incision. Reducing the content of the hernia sac and dissecting it. By using endo-fascial closure under direct vision, introducing the endo-fascial closure from the fascial surface to the intraperitoneal, then holding the sutures outside the fascia, and then sliding the lower half of mesh intraperitoneally by pulling lower half sutures at the same time. After inserting the whole mesh intraperitoneally, we catch the upper half mesh sutures and pull them through the fascia. The parachuting technique involves pulling all sutures at the same time to expand the mesh intraperitoneally, confirming the mesh covering the umbilical defect, 3 cm apart, and the supraumbilical incision. After that, tie the sutures in pairs, 12 o'clock with 6 o'clock sutures, 3 o'clock with 9 o'clock, and then the other corners simultaneously. Defects are found between the sutures fixed with extra interrupted sutures to prevent bowel herniation. Closing the supraumbilical incisional opening by polydioxanone suture after confirming the mesh covering 3 cm above the creating incision. Plication of recti, if diastasis is found, then we continue the abdominoplasty procedure.
Discussion: Umbilical hernia is commonly associated with diastasis of the recti muscles, with a reported incidence of approximately 40–45%, and it is more frequently observed in women than in men. Concomitant repair of umbilical hernia with abdominoplasty, particularly in patients with a pendulous abdomen, has been shown to be a safe procedure that provides superior aesthetic outcomes and significantly improves postoperative quality of life. The sublay preperitoneal mesh technique for umbilical hernia repair demonstrates a low recurrence rate, generally reported to be less than 10%, with a lower incidence of seroma formation compared to onlay mesh repair. Placement of the mesh in the preperitoneal plane allows preservation of the umbilical pedicle blood supply while reinforcing the umbilical defect and strengthening the abdominal wall. We have developed a surgical technique for umbilical hernia repair that is time-efficient, cost-effective, and focused on preserving the vascular supply of umbilical pedicles. We believe that the use of preperitoneal sublay mesh is associated with fewer complications and a lower recurrence rate compared to other techniques. Performing this repair as a single-stage procedure in combination with rectus muscle plication and abdominoplasty offers greater patient comfort and leads to a significant improvement in postoperative quality of life. We do not recommend primary suture closure of the umbilical defect alone, as this may be associated with a higher recurrence rate. Currently, we are prospectively collecting cases performed using this technique to evaluate operative duration, cost, postoperative quality of life, and recurrence rates.
Summary
The parachute technique of sublay intraperitoneal umbilical repair shortens the time of the abdominoplasty procedure. It is easy, fast, and with a low complication rate.
References
- Prevalence and Risk Factors of Hernia in Patients With Rectus Abdominis Diastasis: A 10-Year Multicenter Retrospective Study ,Sue Yuan et al, Frontiers in Surgery,1 September 2021 , Volume 8 ,Article 730875
- Concomitant hernioplasty and abdominoplasty versus hernioplasty of paraumbilical hernia in multiparous women, with pendulous abdomen , Yasser A. Orban et al , The Egyptian Journal of Surgery 40(4):p 1187-1191, October-December 2021.
- Concomitant sublay mesh repair of umbilical hernia and abdominoplasty, McKnight et al , Can J Plast Surg Vol 20 No 4 Winter 2012.
- SUMMER Trial: mesh versus suture repair in small umbilical hernias in adults—a study protocol for a prospective randomized double-blind multicenter clinical trial, Melkemichel et al. Trials (2021) 22:411 ,BMC.