301 posters, 50 videos, 13 topics, 13 sessions, 734 authors, 193 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
ISMICS 2026 Annual Meeting
10 - 13 June, 2026 | Miami, Florida

D177
Development Of Single Incision Minimally Invasive Programs In Congenital Heart Surgery
Poster Presenter
Authors
Ahmed Wahba, Aziza Tavakkalova, Fetoh Alaaeldin, Ahmed E. Elkafoury, Amir Bastawisy
Affiliations
Department of Cardiothoracic Surgery, Faculty of Medicine, Port Said University, Port Said, Egypt, Medical School, Central Asian University, Tashkent, Uzbekistan, Lecturer of Cardiothoracic Surgery, Faculty of Medicine, Mansoura University, Mansoura, Egypt, Department of Cardiac Surgery, Mahalla Heart Center, El-Mahalla El-Kubra, Egypt
Part of Topic
Pediatric - Cardiac, Cardiovascular & Thoracic
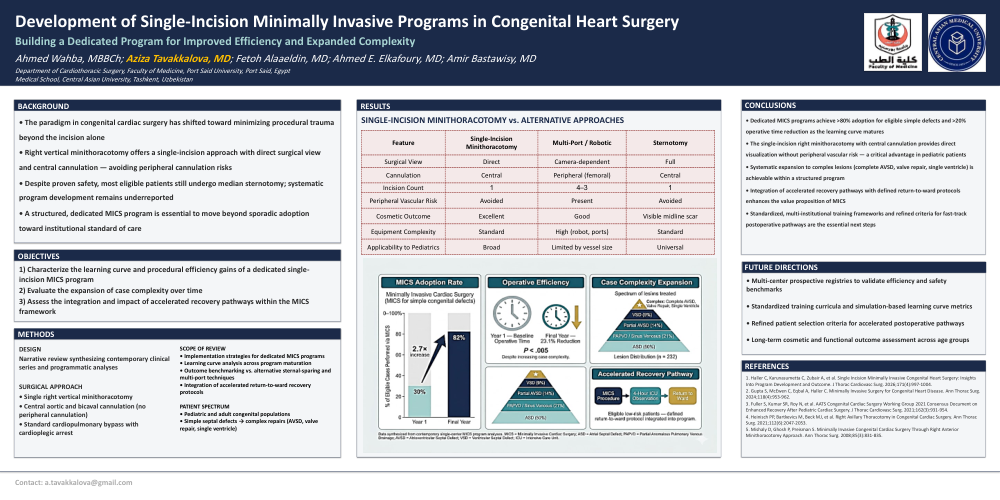
Background: The paradigm in congenital cardiac surgery has shifted toward minimizing procedural trauma. For pediatric and adult congenital populations, this evolution extends beyond incisions to holistic patient management. The systematic development of dedicated single-incision minimally invasive cardiac surgery (MICS) programs, utilizing approaches like the right vertical minithoracotomy, represents a critical advancement.
Methods: This narrative review synthesizes findings from contemporary clinical series and programmatic analyses. It evaluates the implementation, learning curves, and outcomes associated with establishing dedicated MICS programs for congenital heart disease, with focus on the prevalent right minithoracotomy approach which facilitates central cannulation.
Results: Evidence indicates that dedicated MICS programs can achieve significant gains in procedural efficiency, with reported operative time reductions exceeding 20% despite expanding case complexity. Adoption rates for suitable simple defects can surpass 80%. The integration of accelerated recovery pathways, including defined return-to-ward protocols, enhances the value proposition. Compared to alternative multi-port or sternal-sparing techniques, the single-incision minithoracotomy offers a direct surgical view and avoids peripheral cannulation. Application has broadened from simple septal defects to include more complex repairs.
Conclusions: The systematic development of MICS programs facilitates safe expansion to increasingly complex congenital lesions while improving efficiency and enabling fast-track recovery. A structured approach to the learning curve and multidisciplinary pathway development are key. Future multi-institutional studies are needed to standardize training and refine criteria for accelerated postoperative pathways.
Keywords: Minimally Invasive Cardiac Surgery; Congenital Heart Disease; Thoracotomy; Program Development; Fast-Track Recovery; Learning Curve