301 posters, 50 videos, 13 topics, 13 sessions, 734 authors, 193 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
ISMICS 2026 Annual Meeting
10 - 13 June, 2026 | Miami, Florida

P22
Management Of Left Atrial Appendage Exclusion During Maze V Procedure And Cabg
Poster Presenter
Authors
Part of Topic
Arrhythmia Surgery & Interventions
Management Of Left Atrial Appendage Exclusion During Maze V Procedure And Cabg
Amiran Sh. Revishvili, Vadim A. Popov, Egor S. Malyshenko, Maksim A. Anishchenko, Kirill A. Kozyrin, Natalia V. Popova, Madina W.Kadirowa
A.V. Vishnevsky National Medical Research Center of Surgery, Moscow, Russian Federation.
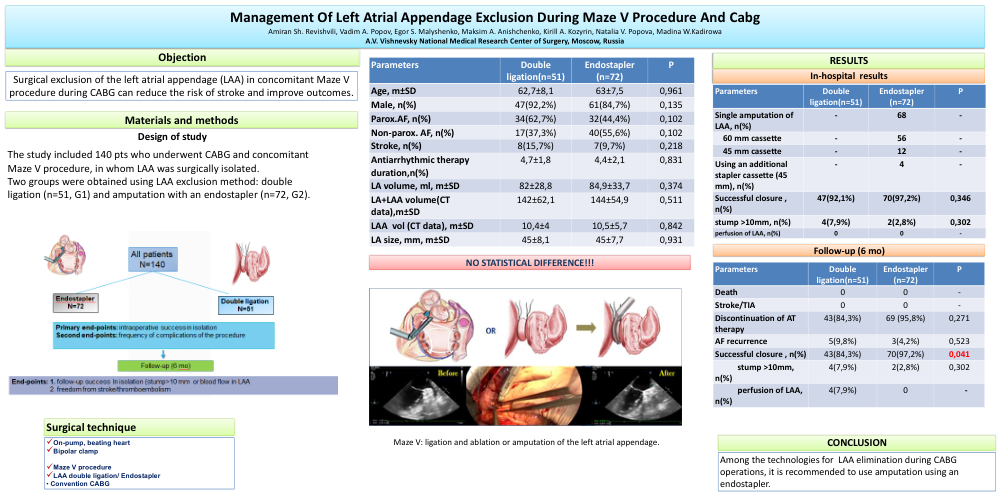
Objective: Surgical exclusion of the left atrial appendage (LAA) in concomitant Maze V procedure during CABG can reduce the risk of stroke and improve outcomes.
Methods: The study included 140 pts who underwent CABG and concomitant Maze V procedure, in whom LAA was surgically isolated. Two groups were obtained using LAA exclusion method: double ligation (n=51, G1) and amputation with an endostapler (n=72, G2). No significant differences were found between groups G1 and G2 in preoperative parameters. The average age was 62±5.6 years, there were 47 men (92.2%) in G1 and 61 men (84.7%) in G2.Non-paroxysmal AF was present in 17(37.1 %) pts in G1 and 40(55.6%) pts in G2. 8 (15.7%) people in G1 and 7(9.7%) had a history of stroke. The effectiveness and safety of removal techniques were evaluated.
Results: All pts in G2 achieved technical success (stamp < 10 mm according to the transesophageal ECHO). 68 pts (94,4%) had a single amputation. An additional cassette (45mm) was used in four pts (5.6%). There were no cases of injuries or bleeding caused by the use of an endostapler. 47 (92.1%) pts in G1 had intraoperative success in isolation. 4 (7.9%) pts had a stump larger than 10 mm. According to transesophageal ECHO, no signs of thrombosis were detected after 6 months. There were no cases of stroke and embolisms in follow-up. Anticoagulant therapy was discontinued in 43 (84.3%) pts in G1 and 69 (95.8%) pts in G2 (p=0.271).Successful isolation of LAA was achieved in 43 (84.3%) pts in G1 and 70 (97.2%) in G2 (p=0.041). A stump >10 mm was observed in 4 (7.9%) pts in G 1 and 2 (2.8%)pts in G2 (p=302). In G1 blood flow in LAA was preserved in 4 (7.9%) pts. This was not the case in G2.
Conclusions: Among the technologies for LAA elimination during CABG operations, it is recommended to use amputation using an endostapler