301 posters, 50 videos, 13 topics, 13 sessions, 734 authors, 193 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
ISMICS 2026 Annual Meeting
10 - 13 June, 2026 | Miami, Florida

P15
Robotic-assisted 3 D Mapping And Targeted Ablation Of Early Pulse Field Ablation Failure For Persistent Atrial Fibrillation
Poster Presenter
Authors
Stefano Schena, Anne Koenigs, James Oujiri, Marcie Berger, Mario Gasparri
Affiliations
Division of Cardiothoracic Surgery, Froedtert Hospital & Medical College of Wisconsin, Milwaukee, WI, Department of Cardiovascular Medicine, Section of Cardiac Electrophysiology, Froedtert Hospital & Medical College of Wisconsin, Milwaukee, WI
Part of Topic
Arrhythmia Surgery & Interventions
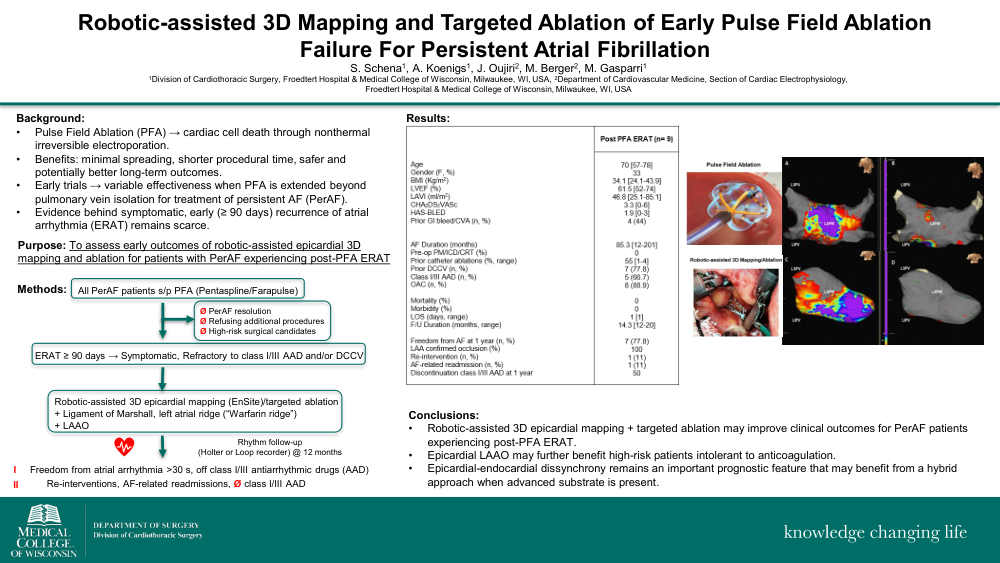
Background: Pulse Field Ablation (PFA) achieves cardiac cell death through nonthermal irreversible electroporation with minimal spreading, shorter procedural times, safer and potentially better long-term outcomes than traditional thermal energies. Early trials suggest variable effectiveness when PFA is extended beyond pulmonary vein isolation for treatment of persistent AF (PerAF). Data and pathophysiological mechanism for symptomatic, early (<90 days) recurrence of atrial arrhythmia (ERAT) remain scarce. Aim of this study was to assess early outcomes of robotic-assisted epicardial 3D mapping/ablation for patients with PerAF experiencing post-PFA ERAT.
Methods: Consecutive patients with symptomatic PerAF, refractory to class I/III antiarrhythmic drugs (AAD) and/or cardioversion, who underwent ablation using a standard pentaspline catheter with Farapulse technology. Bidirectional block was confirmed in all cases. Robotic-assisted 3D epicardial mapping/targeted ablation was considered as rescue treatment strategy of ERAT. Division of the ligament of Marshall, ablation of the left atrial ridge and epicardial LAAO were also performed. Patient follow-up consisted of 3- and 12-month visits with Holter monitoring and cardiac CTA. Primary endpoint was procedural safety and freedom from atrial arrhythmia >30s, off class I/III AAD at 12 months. Secondary endpoint was assessment of re-interventions, AF-related readmissions, and AAD discontinuation.
Results: Between May and December 2024, 9 patients (mean age 70, 33% F - Table) experienced ERAT following PFA. The mean recurrence period was 11 weeks. Following epicardial mapping, residual non-PV triggers were found in all patients with aspecific distribution (Figure 1). All patients underwent successful epicardial ablation. Median LOS was 1 day without intra- or periprocedural morbidity or mortality. Mean follow-up was 14 months. One patient was readmitted within 1 week for paroxysmal AF and one patient experienced atrial flutter requiring reintervention at 8 months. Freedom from AF was observed in 7 patients (77.8%) at 12 months. Class I/III AAD discontinuation occurred in 50% of cases.
Conclusions: Robotic-assisted 3D epicardial mapping and targeted ablation may improve clinical outcomes for PerAF patients experiencing post-PFA ERAT. Epicardial LAAO may further benefit high-risk patients intolerant to anticoagulation. These initial findings confirm that epicardial-endocardial dissynchrony remains an important prognostic feature that may benefit from a hybrid approach when advanced substrate is present.
