301 posters, 50 videos, 13 topics, 13 sessions, 734 authors, 193 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
ISMICS 2026 Annual Meeting
10 - 13 June, 2026 | Miami, Florida

P105
Minimally Invasive Lung Nodule Resection Utilizing Electromagnetic Navigational Bronchoscopy Dye Marking: 100 Consecutive Cases
Poster Presenter
Authors
Affiliations
null,
Part of Topic
Thoracic Surgery � Lung
Electromagnetic navigational bronchoscopy (ENB) provides real-time localization of peripheral lung nodules and, when combined with robotic-assisted thoracic surgery, compensates for the lack of tactile feedback to enable precise intraoperative nodule identification. We report outcomes from the first 100 consecutive robotic lung nodule resections performed using ENB dye marking.
This is a single-center retrospective review of 100 consecutive patients who underwent ENB-guided dye marking followed by robotic-assisted resection. ENB was performed by two fellowship-trained interventional pulmonologists using the Johnson & Johnson Monarch platform. Pulmonary nodules were dual-labeled with methylene blue and indocyanine green to facilitate localization. Cases were stratified into sequential tertiles (1–33, 34–66, and 67–100) to assess trends in operative efficiency and perioperative outcomes. The primary outcomes were successful nodule localization and dye-marking time. The learning curve was characterized by fitting dye-marking time to an exponential decay model to identify the plateau point.
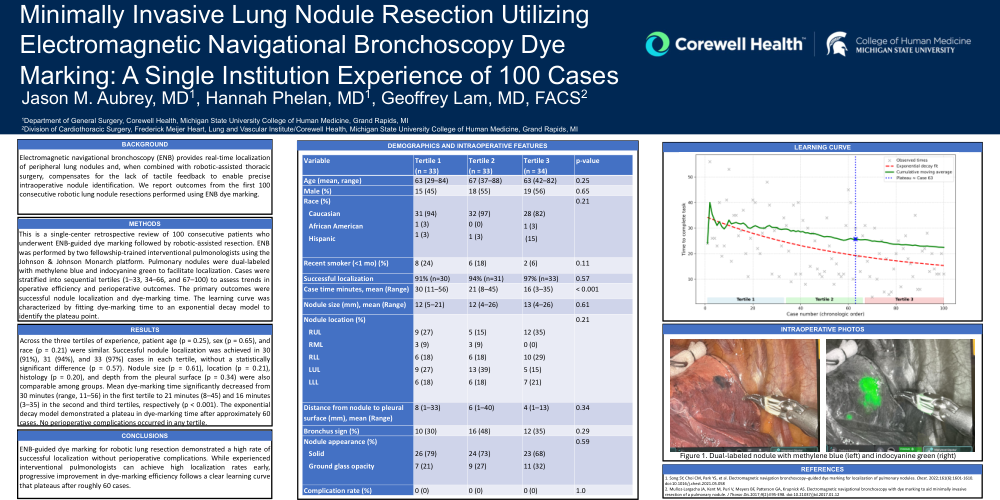
Across the three tertiles of experience, patient age (p = 0.25), sex (p = 0.65), and race (p = 0.21) were similar. Successful nodule localization was achieved in 30 (91%), 31 (94%), and 33 (97%) cases in each tertile, without a statistically significant difference (p = 0.57). Nodule size (p = 0.61), location (p = 0.21), histology (p = 0.20), and depth from the pleural surface (p = 0.34) were also comparable among groups. Mean dye-marking time significantly decreased from 30 minutes (range, 11–56) in the first tertile to 21 minutes (8–45) and 16 minutes (3–35) in the second and third tertiles, respectively (p < 0.001). The exponential decay model demonstrated a plateau in dye-marking time after approximately 60 cases. No perioperative complications occurred in any tertile.
ENB-guided dye marking for robotic lung resection demonstrated a high rate of successful localization without perioperative complications. While experienced interventional pulmonologists can achieve high localization rates early, progressive improvement in dye-marking efficiency follows a clear learning curve that plateaus after roughly 60 cases.