395 posters, 1 audios, 13 topics, 29 sessions, 1,056 authors, 461 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
51st Annual Regional Anesthesiology and Acute Pain Medicine Meeting
April 16 - 18, 2026 | Phoenix, Arizona

2311793
Stellate Ganglion Block for the Treatment of Refractory Ventricular Tachycardia Storm
Poster Presenter
Authors
Affiliations
Part of Topic
Medically Challenging Cases
-
Stellate ganglion blocks (SGB) have been shown to be useful as a minimally invasive treatment for a range of high-morbidity disease processes associated with increased sympathetic activation including PTSD and postherpetic neuralgia1
-
SGB is an emerging treatment option for the suppression of ventricular tachycardia (VT) storm, a high-mortality rhythm characterized by ≥3 episodes of of ventricular arrhythmia within 24 hours1,2
-
This poster highlights a case of SGB use for the treatment of unstable ventricular tachyarrhythmia refractory to conventional treatment options
-
In this case, the SGB was a successful temporizing measure in restoring hemodynamic stability
-
SGB allowed the patient to undergo ECMO cannulation in a controlled operating room setting rather than emergently at the bedside
-
This case highlights the utility of SGB for VT refractory to multiple treatment modalities, serving as a bridge to MCS initiation and ultimately transplantation
-
A 50-year-old male with a history of cardiomyopathy (EF 20%) complicated by VT with subsequent ICD placement and multiple prior VT ablations was admitted to the ICU with >10 ICD shocks at home; the patient was found to be in recurrent VT.
-
He was treated with amiodarone, procainamide, and lidocaine infusions, underwent multiple VT ablations and anti-tachycardia pacing (ATP). Despite these interventions, he was unable to convert to sinus rhythm.
-
The patient developed pulmonary edema and signs of end organ dysfunction; he then underwent intraaortic balloon pump (IABP) placement and multiple cardioversions without resolution of VT.
-
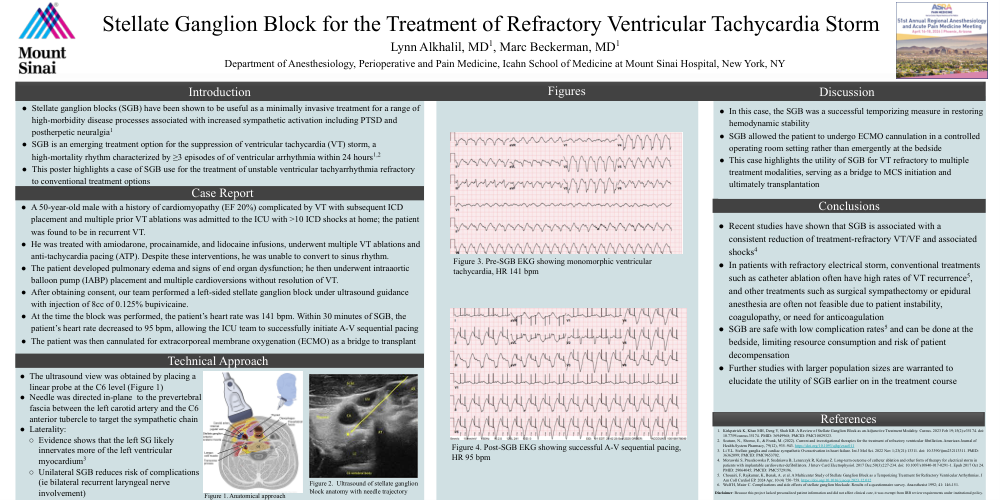
After obtaining consent, our team performed a left-sided stellate ganglion block under ultrasound guidance with injection of 8cc of 0.125% bupivicaine.
-
At the time the block was performed, the patient’s heart rate was 141 bpm. Within 30 minutes of SGB, the patient’s heart rate decreased to 95 bpm, allowing the ICU team to successfully initiate A-V sequential pacing
-
The patient was then cannulated for extracorporeal membrane oxygenation (ECMO) as a bridge to transplant
-
The ultrasound view was obtained by placing a linear probe at the C6 level (Figure 1)
-
Needle was directed in-plane to the prevertebral fascia between the left carotid artery and the C6 anterior tubercle to target the sympathetic chain
-
Laterality:
-
Evidence shows that the left SG likely innervates more of the left ventricular myocardium3
-
Unilateral SGB reduces risk of complications (ie bilateral recurrent laryngeal nerve involvement)