395 posters, 1 audios, 13 topics, 29 sessions, 1,056 authors, 461 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
51st Annual Regional Anesthesiology and Acute Pain Medicine Meeting
April 16 - 18, 2026 | Phoenix, Arizona

2317347
Fractionated vs single-shot intrathecal bupivacaine for cesarean delivery: A systematic review and meta-analysis
Poster Presenter
Authors
Affiliations
Part of Topic
Scientific Abstracts > Regional Anesthesia
Background
Spinal anesthesia is the most commonly used technique for cesarean delivery but is frequently complicated by maternal hypotension due to sympathetic blockade1,2. Although vasopressors are routinely used, techniques that improve hemodynamic stability remain clinically relevant. Fractionated intrathecal dosing may attenuate hypotension by reducing abrupt sympathetic block. Therefore, we compared fractionated versus single-shot intrathecal hyperbaric bupivacaine for cesarean delivery, focusing on maternal hemodynamic stability and block performance.3
Materials and Methods
We searched PubMed, Embase, Cochrane Library, Web of Science, and Google Scholar through October 2025 for randomized controlled trials (RCTs) in women undergoing cesarean delivery under spinal anesthesia, comparing fractionated and single-shot intrathecal 0.5% hyperbaric bupivacaine. The primary outcome was maternal hypotension; secondary outcomes included vasopressor requirement, sensory and motor onsets, and the durations of postoperative analgesia and sensory and motor blocks. The heterogeneity was quantified by I². Trial sequential analysis (TSA) and leave-one-out sensitivity analyses were prespecified.
Results/Case Report
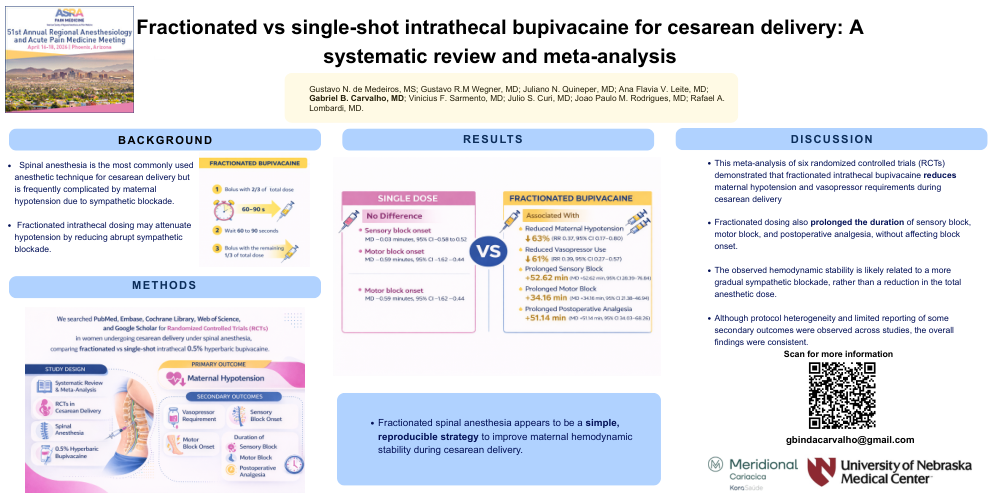
Six RCTs were included, encompassing 520 patients. Fractionated bupivacaine was associated with reduced maternal hypotension (RR 0.37, 95% CI 0.17–0.80) and vasopressor use (RR 0.39, 95% CI 0.27–0.57), while onset times for sensory (MD −0.03 minutes, 95% CI −0.58 to 0.52) and motor blocks (MD −0.59 minutes, 95% CI −1.62 to 0.44) had no difference between groups. Additionally, the fractionated technique significantly prolonged the duration of sensory block (MD +52.62 min, 95% CI 28.39–76.84), motor block (MD +34.16 min, 95% CI 21.38–46.94), and postoperative analgesia (MD +51.14 min, 95% CI 34.03–68.26). Compared with a single-shot, fractionated intrathecal hyperbaric bupivacaine for cesarean delivery reduces maternal hypotension and vasopressor requirements while prolonging sensory, motor and analgesia durations without affecting block onset. Findings support fractionated dosing as a simple strategy to improve hemodynamic stability.
Discussion
In this meta-analysis of six RCT's, fractionated intrathecal bupivacaine reduced maternal hypotension and vasopressor requirements, findings confirmed by trial sequential analysis. Fractionation also prolonged sensory, motor, and analgesic block duration without affecting onset.These effects likely result from a more gradual sympathetic blockade rather than a reduction in anesthetic dose. Despite protocol heterogeneity and limited reporting of secondary outcomes, fractionated spinal anesthesia appears to be a simple, reproducible strategy to improve hemodynamic stability during cesarean delivery.