395 posters, 1 audios, 13 topics, 29 sessions, 1,056 authors, 461 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
51st Annual Regional Anesthesiology and Acute Pain Medicine Meeting
April 16 - 18, 2026 | Phoenix, Arizona

2315127
Standardizing Pre-operative Consent for Truncal Blocks in Thoracic Surgery: A Quality Improvement Project
Poster Presenter
Authors
Nicholas Wegener, Connor Singrey, Dong Ho Shin, Jiayi Hu, Diego Bauza, Shelby Badani
Affiliations
Part of Topic
Safety/QA/QI Projects
Introduction:
Intra-operative consultations for truncal blocks occur when surgeons convert a robotic or laparoscopic surgery to open.
Obtaining consents for these blocks warrants ethical and medicolegal considerations.
Surrogate decision-makers are often consented or the patient is consented in recovery. [1]
The risks associated with single-shot nerve blocks are low. BUT patients are not necessarily consenting to single-shot nerve blocks when consenting for anesthesia. [2]
Patients who were not consented pre-operatively can result in a delay in patients receiving an analgesic block.
Presents challenges to the acute pain service workflow.
Materials and Methods:
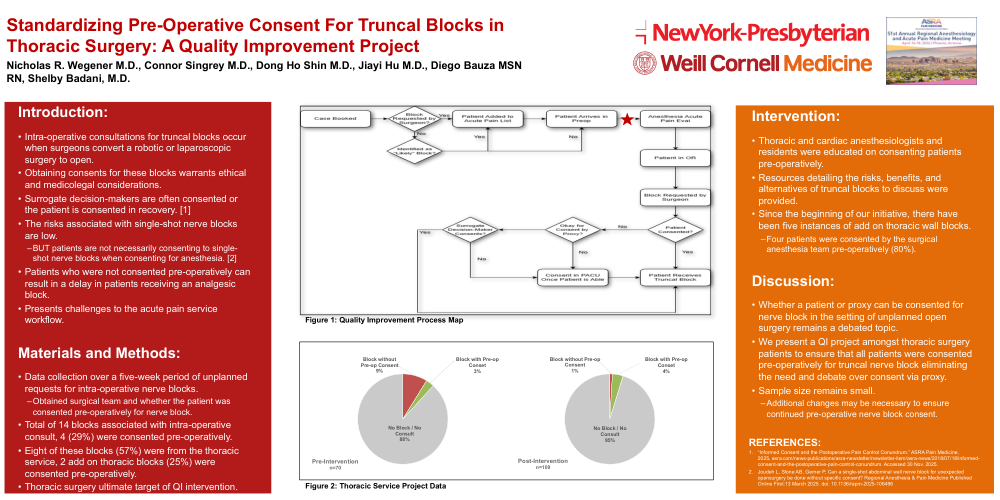
Data collection over a five-week period of unplanned requests for intra-operative nerve blocks. Obtained surgical team and whether the patient was consented pre-operatively for nerve block.
Total of 14 blocks associated with intra-operative consult, 4 (29%) were consented pre-operatively.
Eight of these blocks (57%) were from the thoracic service, 2 add on thoracic blocks (25%) were consented pre-operatively.
Thoracic surgery ultimate target of QI intervention.
Intervention:
Thoracic and cardiac anesthesiologists and residents were educated on consenting patients pre-operatively.
Resources detailing the risks, benefits, and alternatives of truncal blocks to discuss were provided.
Since the beginning of our initiative, there have been five instances of add on thoracic wall blocks. Four patients were consented by the surgical anesthesia team pre-operatively (80%).
Discussion:
Whether a patient or proxy can be consented for nerve block in the setting of unplanned open surgery remains a debated topic.
We present a QI project amongst thoracic surgery patients to ensure that all patients were consented pre-operatively for truncal nerve block eliminating the need and debate over consent via proxy.
Sample size remains small. Additional changes may be necessary to ensure continued pre-operative nerve block consent.
REFERENCES:
- “Informed Consent and the Postoperative Pain Control Conundrum.” ASRA Pain Medicine, 2025, asra.com/news-publications/asra-newsletter/newsletter-item/asra-news/2018/07/18/informed-consent-and-the-postoperative-pain-control-conundrum. Accessed 30 Nov. 2025.
- Joudeh L, Stone AB, Gerner P, Can a single-shot abdominal wall nerve block for unexpected opensurgery be done without specific consent? Regional Anesthesia & Pain Medicine Published Online First:13 March 2025. doi: 10.1136/rapm-2025-106496