206 posters, 13 topics, 5 sessions, 713 authors, 294 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
AAPS 104th Annual Meeting
May 2-5, 2026 | Lihue, HI

D125
Outcomes Of Robotic Versus Open Parastomal Hernia Repair: A Propensity Score-matched Analysis
Poster Presenter
Authors
Gabriel De la Cruz Ku, Anshumi Desai, Jiddu Guart, Alba Zevallos, Martin Hemeryth, Flavia Rioja, Joseph M. Escandón, Sarah Roberts, Camila Amado Rottier, Natalia Mejia, Jose Luis Barrueto-Deza, Camila Franco, Adam Walchak, Adam Walchak
Affiliations
Temple University Hospital, Universidad Cientifica del Sur, Lima, Peru,
Part of Topic
General Reconstruction
Background
• Parastomal hernia (PSH) is a common complication following stoma formation, with an incidences of 30–50%, and is associated with significant morbidity, including pain, appliance difficulties, and impaired quality of life.
• In the emergency setting, PSH may present with obstruction, incarceration, or ischemia, often requiring urgent surgical intervention.
• Open repair is the standard approach but is associated with high morbidity, prolonged length of stay, and recurrence rates of up to 45%
• Minimally invasive approaches have been increasingly adopted to improve outcomes
Objectives
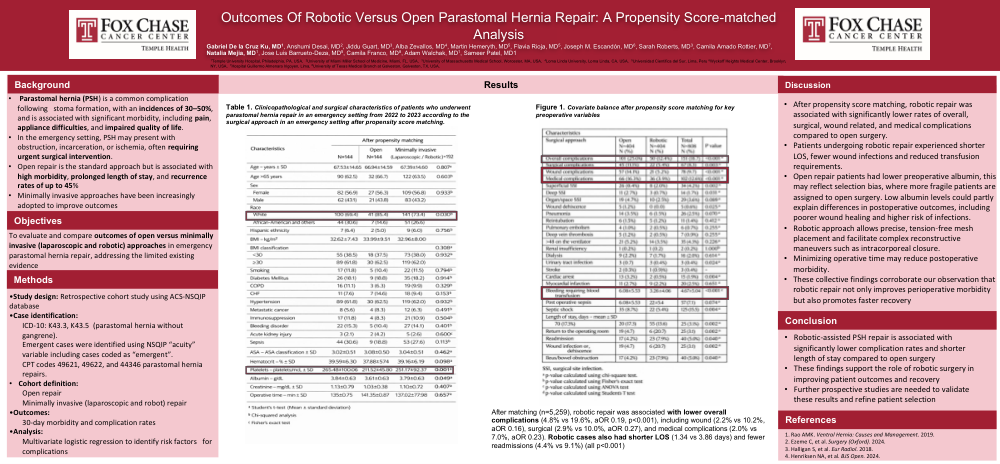
To evaluate and compare outcomes of open versus minimally invasive (laparoscopic and robotic) approaches in emergency parastomal hernia repair, addressing the limited existing evidence
Methods
• Study design: Retrospective cohort study using ACS-NSQIP database
• Case identification:
ICD-10: K43.3, K43.5 (parastomal hernia without gangrene).
Emergency cases were identified using NSQIP “acuity” variable including cases coded as “emergent”.
CPT codes 49621, 49622, and 44346 parastomal hernia repairs.
• Cohort definition:
Open repair
Minimally invasive (laparoscopic and robot) repair
• Outcomes:
30-day morbidity and complication rates
• Analysis:
Multivariate logistic regression to identify risk factors for complications
Discussion
• After propensity score matching, robotic repair was associated with significantly lower rates of overall, surgical, wound related, and medical complications compared to open surgery.
• Patients undergoing robotic repair experienced shorter LOS, fewer wound infections and reduced transfusion requirements.
• Open repair patients had lower preoperative albumin, this may reflect selection bias, where more fragile patients are assigned to open surgery. Low albumin levels could partly explain differences in postoperative outcomes, including poorer wound healing and higher risk of infections.
• Robotic approach allows precise, tension-free mesh placement and facilitate complex reconstructive maneuvers such as intracorporeal closure.
• Minimizing operative time may reduce postoperative morbidity.
• These collective findings corroborate our observation that robotic repair not only improves perioperative morbidity but also promotes faster recovery
Conclusion
• Robotic-assisted PSH repair is associated with significantly lower complication rates and shorter length of stay compared to open surgery
• These findings support the role of robotic surgery in improving patient outcomes and recovery
• Further prospective studies are needed to validate these results and refine patient selection