395 posters, 1 audios, 13 topics, 29 sessions, 1,056 authors, 461 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
51st Annual Regional Anesthesiology and Acute Pain Medicine Meeting
April 16 - 18, 2026 | Phoenix, Arizona

2316138
Sacral Erector Spinae Plane Block for Gluteal Sarcoma Resection
Poster Presenter
Authors
Affiliations
Part of Topic
Medically Challenging Cases
Surgical incisions involving the posterior gluteal regional have been a difficult area for regional anesthesia to treat. Neuraxial techniques carry increased risks of hypotension and also require monitoring of coagulation status. Additionally, neuraxial techniques can limit neurological monitoring. This case presents a patient who received a single shot sacral erector spinae plane (ESP) block for resection of a sarcoma in the posterior gluteal region. (64/75 words)
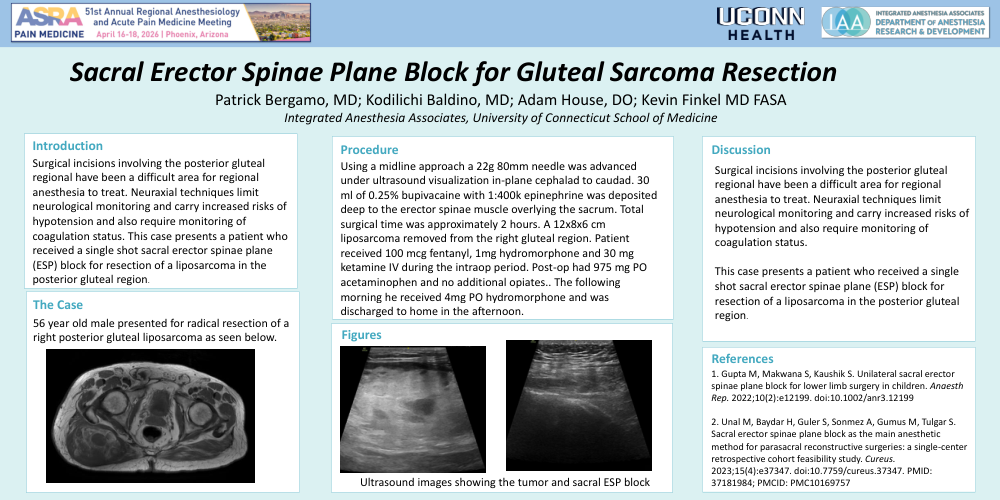
The patient is a 56 year old male (154 cm, 61kg) with history of hypertension, kidney disease on dialysis, and heart failure who presented for radical resection of a right posterior gluteal liposarcoma. The patient was positioned prone, monitors and supplemental oxygen were attached and pt received 2mg midazolam IV. Using a midline approach a 22g 80mm needle was advanced under ultrasound visualization in-plane cephalad to caudad. 30 ml of 0.25% bupivacaine with 1:400k epinephrine was deposited deep to the erector spinae muscle overlying the sacrum, with appropriate spread confirmed under ultrasound. A neurological exam was performed immediately afterwards with no concern for intrathecal or epidural spread. Intraoperatively, the patient had general anesthesia with an endotracheal tube. Total surgical time was approximately 2 hours during which the patient had a 12x8x6 cm liposarcoma removed from the right gluteal region. Blood loss was 100 ml. Patient received 100 mcg fentanyl, 1mg dilaudid and 30 mg ketamine IV during the intraop period. In the anesthesia recovery unit the patient had 975 mg PO acetaminophen and no additional opiates. The patient had a normal neurological exam post-operatively. The following morning he received 4mg PO hydromorphone and was discharged to home in the afternoon. (200/200 words)
The ESP block has been described for use in many types of surgeries. The sacral ESP block is a relatively newer block that can provide analgesia bilaterally with a single injection, avoids hypotension, and does not effect neuromonitoring. Intravascular injection is rare given there are no large vessels and the sacrum provides a backstop to limit damage to underlying structures. This case demonstrates that the sacral ESP block can be used for gluteal surgical incisions